Friday, 20 March 2020

Food shaming is not a game

Posted by Sarah Dempster, Registered Nutritionist (Public Health)

“Our current learning focus is food. We are exploring what makes a food healthy / unhealthy” says the notice board in the entrance to my daughter’s nursery. I sigh. Is this a battle I want to pick? I already had some difficult words with the Head Teacher last year about food-based rewards, and I don’t really want to become known as that mum who complains about every food-related activity that happens in the school. Especially when people don’t seem to get what it is that I’m actually complaining about.

I’ve worked in and around public health nutrition for ten years. Over the past few years - probably since having children of my own - I’ve become increasingly concerned about the way we communicate to children about food. Take this “teacher tested” educational game for four to eight year olds as an example:


I wonder if, in our worthy quest to do everything we can to improve children’s eating patterns, some of the things we say and do are having unintended consequences. What might be the impact of teaching nursery-age children to polarise foods into “unhealthy” versus “healthy” categories? What are we saying when we imply that people who eat so-called “junk” foods like burgers or pizza are “greedy”? What happens in children’s minds when they’re presented with those same “unhealthy” or “junk” foods as a reward for good behaviour? Or when their parent’s food choices are so constrained that a hotdog is the only option for dinner?

Mixed messages

My biggest concern relates to the disconnect between nutrition education and children’s day-to-day experiences of food. One UK study involving 9-10-year olds showed that children have difficulty interpreting healthy eating messages. An example quote was:
“it’s not true that chocolate’s bad for you because I eat chocolate, and I’m not completely fat, am I?” (Fairbrother, Curtis, & Goyder, 2016, p. 481)
Overall, it is thought that what children believe and know from their own experiences about food has a greater influence on their eating behaviours than what they are taught (Schultz & Danford, 2016). This makes me wonder why we’re teaching children about “healthy eating” at a young age at all - shouldn’t we just be showing them through the experiences we facilitate and/or provide for them and their families? 

What do children understand from nutrition education?

Health is an abstract concept and we know that young children are concrete thinkers. While they may be able to categorise foods as “healthy” or “unhealthy” by rote in pre-school, they are unlikely to make sense of why each food is in each category. They can understand that food provides energy but it isn’t until they are much older that they can accurately explain physiological reasons for eating (Inagaki & Hatano, 2006; Nguyen, Gordon, & McCullough, 2011; Slaughter & Ting, 2010). They find the concept of “prevention” particularly difficult (Legare & Gelman, 2014).

There’s little research on the impact this may have. However, Pinhas et al. (2013) found some evidence that healthy eating lessons could trigger eating disorder development in susceptible children, who may become preoccupied with food after learning about nutrition. We know that children are under pressure to conform to the “thin ideal” body type from a young age. One Australian study found that 34% of 5-year old girls were already restricting food (Damiano et al., 2015). Meanwhile, children demonstrate anti-fat attitudes from as early as two years old (Di Pasquale & Celsi, 2017). Oversimplifying the relationship between food and size in a game like Greedy Gorilla will at best be ineffective and at worst, fuel the well-known negative consequences of weight stigma (World Health Organization, 2017).

What does the curriculum actually say?

Food and nutrition is a focus area in UK curriculum frameworks, with defined knowledge and skills outcomes at specific ages or stages. Food literacy is covered in a much broader way than just teaching kids what to eat for health. This provides the opportunity for rich, multi-sensory learning experiences… how food is grown, how people from different countries and cultures eat, what different foods look, smell and taste like, how to prepare foods… and as children get older, bringing in critical appraisal around what influences our food choices (e.g. social, health-related or financial factors, the food industry, diet culture). There are lots of examples of good practice around this and it can be done in very positive and inclusive ways.

Until recently, there was little evidence of moralistic language such as “junk food” or reference to “unhealthy eating” within the curriculum. However, the Department for Education (2019) now states that by the end of primary school, children should know: “the characteristics of a poor diet and risks associated with unhealthy eating (including, for example, obesity)”. This worries me, especially for young children who are dependent on adults for all the food they consume, and because we know that weight bias is prevalent in education settings (Nutter et al., 2019).

Food education is really important for young children, but I think we need to look at how public health and education professionals collaborate to get it right for all children. This means improving our understanding of the impact of the language we use, to ensure that we are not fuelling fear, shame or stigma around food or body size.


References:
  1. Fairbrother, H., Curtis, P., & Goyder, E. (2016). Making health information meaningful: Children’s health literacy practices. SSM - Population Health, 2, 476–484. https://doi.org/10.1016/j.ssmph.2016.06.005 
  2. Schultz, C. M., & Danford, C. M. (2016). Children’s knowledge of eating: An integrative review of the literature. Appetite. https://doi.org/10.1016/j.appet.2016.08.120 
  3. Inagaki, K., & Hatano, G. (2006). Young Children’ s Conception of the Biological World. Current Directions in Psychological Science, 15(4), 177–181. https://doi.org/10.1111/j.1467-8721.2006.00431.x
  4. Nguyen, S. P., Gordon, C. L., & McCullough, M. B. (2011). Not as easy as pie. Disentangling the theoretical and applied components of children’s health knowledge. Appetite, 56(2), 265–268. https://doi.org/10.1016/j.appet.2011.01.008 
  5. Slaughter, V., & Ting, C. (2010). Development of ideas about food and nutrition from preschool to university. Appetite, 55(3), 556–564. https://doi.org/10.1016/j.appet.2010.09.004 
  6. Legare, C. H., & Gelman, S. A. (2014). Examining Explanatory Biases in Young Children’s Biological Reasoning. Journal of Cognition & Development, 15(2), 287–303. https://doi.org/10.1080/15248372.2012.749480 
  7. Pinhas, L., McVey, G., Walker, K. S., Norris, M., Katzman, D., & Collier, S. (2013). Trading Health for a Healthy Weight: The Uncharted Side of Healthy Weight Initiatives. Eating Disorders, 21(2), 109–116. https://doi.org/10.1080/10640266.2013.761082 
  8. Damiano, S.R., Paxton, S.J., Wertheim, E.H., McLean, S.A. & Gregg, K.J. (2015) Dietary restraing of 5-year old girls: Associations with internalization of the thin ideal and maternal, media and peer influences. International Journal of Eating Disorders, 48: 1166-1169. https://doi.org/10.1002/eat.22432
  9. Di Pasquale, R. & Celsi, L. (2017) Stigmatization of Overweight and Obese Peers among Children. Frontiers in Psychology. https://doi.org/10.3389/fpsyg.2017.00524 
  10. World Health Organization (2017). Weight bias and obesity stigma: considerations for the WHO European Region. WHO: Geneva. http://www.euro.who.int/en/health-topics/noncommunicable-diseases/obesity/publications/2017/weight-bias-and-obesity-stigma-considerations-for-the-who-european-region-2017)
  11. Department for Education (2019) Relationships Education, Relationships and Sex Education (RSE) and Health Education: Statutory guidance for governing bodies, proprietors, head teachers, principals, senior leadership teams, teachers. Department for Education: London. https://assets.publishing.service.gov.uk/government/uploads/system/uploads/attachment_data/file/805781/Relationships_Education__Relationships_and_Sex_Education__RSE__and_Health_Education.pdf
  12. Nutter, S., Ireland, A., Alberga, A.S., et al. (2019). Weight Bias in Educational Settings:a Systematic Review.Current Obesity Reports, 8, 185-200. https://link.springer.com/content/pdf/10.1007/s13679-019-00330-8.pdf#page32

Thursday, 12 March 2020

A decade of school food policy inertia

To mark International School Meals Day, we asked former-schoolteacher turned school food researcher Kelly Rose from Teesside University to reflect back on the progress of school food over the last decade.


As a former schoolteacher, now researching the secondary school food environment and adolescent dietary habits, it seems fitting to mark school meals day 2020 by reflecting on a decade of secondary school food policy.

Of late, ‘other’ focuses you could say, have overshadowed the important fact that our young people’s diets are nutritionally poor in the UK. But that begs the question, why are the population of future parents and workforce not a priority at all times?

Currently more than 91 million school children around the world are reported to be living with obesity, with the UK being in the top 20 countries for childhood obesity levels, doubling during the primary school years and increasing further into secondary education. The majority of adolescents in the UK have nutrient deficient diets, high in processed foods and very low in fruit and vegetables. With only 4% of teenagers meeting UK public health fibre recommendations, a significant concern given that dietary fibre is linked to a decreased risk of heart disease, type 2 diabetes and cancers. Furthermore, the health inequalities gap is a devastating burden of poor health for our children living in more disadvantaged areas and minority communities, in comparison to those from more affluent areas.

"In my research I have noticed a level of inertia on the evaluation or policing of school food policy this decade"

In my research I have noticed a level of inertia on the evaluation or policing of school food policy this decade, impacting on school’s healthy food choice offerings. Only the other day my friends 11-year-old daughter explained to me the best thing about her new (secondary) school was the food; “I can eat pizza and cookies every day” - oh dear. Kind of explains why our young people are generally low in at least five micronutrients essential for growth, development mood, reproductive health, energy levels and immunity.

2009 – The Nutrient based standards (NBS)

In 2009 the NBS were rolled out to secondary schools in England, after first being introduced into primary schools. Not only were these food standards focused on meeting young people’s nutrient requirements, but also the mapping of 4 areas of influence provided a framework for which to apply the policy across the nation (Haroun et al 2011). These were considered ‘the most detailed and comprehensive in the world’ (Harper and Wells 2007; Evans and Harper 2009). Plus the Initial evaluations were encouraging (Adamson et al 2013; Stevens et al 2013). However, the NBS was for some a ‘complex task’ to implement (Rose et al 2019).

What happened in 2010?

A change in government (the introduction of the Coalition led by David Cameron) meant a change to school food. Firstly, any ‘newly established academies and free schools’ were not required to adhere to the NBS. A decision which some viewed as a deregulation of school food. Quite soon, school food standards were under review, and in 2013 the School Food plan (SPF) developed by Henry Dimbleby and John Vincent (Long, 2019) was introduced.

The School Food Plan

Over the next few years we see SFP replacing NBS as a legal requirement for ‘all food served in most schools’ (Rose et al 2019). Remember the decision in 2010 to release the new academies and free schools? Well, this means that these schools are still exempt from following the standards, however, some have signed up voluntarily. The aim of the SPF is to transform what children are eating in school and to support schools to create a ‘healthy school ethos’. The SFP is certainly visual, providing ease of use, and the comprehensive resources give schools checklists and guidance. But, here lies a problem, where is the school support system?

Part two of the decade

The first chapter of the UK childhood obesity strategy published in 2016 (DHSC, 2016) provided some recommendations and support for school health initiatives, for the most part within primary aged children. Then in 2017 two things of note happened. The School Food Trust integral to the systems mapping approach of the NBS had been an independent organisation since 2011 providing school resources and opportunities for research closed without funds to carry on. The second was an independent review (the Food Education and Learning Landscape review (FELL)) carried out by The Jamie Oliver Food Foundation. The researcher reported a vast difference in the approach to healthy eating and food education in secondary school environments, stating to be ‘alarmed’ at the state of the problems surrounding the “secondary school food environment”.

Chapter two of the Childhood Obesity strategy (DHSC, 2018) included a pledge to commit to support ‘all children with high quality nutrition’ by conducting consultations on nutrition within buying standards for school catering services and introducing ‘a healthy rating scheme’ allowing for ‘self-evaluation’, whilst also providing a more robust Ofsted framework. My issue as a former food and nutrition teacher/head of health education in a school with supportive leadership is that schools need support externally to evaluate and help develop menus and implement nutritious school meals. The capacity, knowledge and often willingness of school leads, along with the lack of monitoring of adherence to school food standards remain huge barriers to effective school food provision.

2020 current picture

This is where we find the current school food picture in England, no real change from 2018. Awaiting the healthy school’s framework and a priority to be placed on school food provision policy. And, in the meantime social norms of poor teen diets are becoming more and more acceptable, healthy food is so ‘uncool’ to a teenager’s street cred. With the myriad of fast food options on the ‘School fringe’ less expensive and more convenient, thus appealing to the innate biology and the impulsivity of teenagers. A plan to shift teen risk perception of unhealthy eating (i.e. behaviour change) as well as consistency in following the SFP is needed.

A big question

The big question here is why has there been no evaluation of the SFP? There is limited evidence of schools following the school food plan. School staff and leaders have in my mind the most strenuous roles in terms of juggling priorities and educating young people. To expect schools to take on the huge role of making sure food provision meet the nutrient requirements of the nations young people without support is to my mind crazy and as we see presently, will not work…


About Kelly:

Kelly is a registered nutritionist and a former school teacher, currently investigating ways to reduce the obesogenic environment with a secondary school food focus as part of her PhD. She is passionate about the impact of nutrition on adolescent health and has spoken locally, nationally and internationally on the topic of school interventions and the importance of social influence on food choice and the impact of nutrition on mood and behaviour. Kelly is registered with the Association for Nutrition (AFN), a member of Plant based health professionals UK, Nutrition Society, British Nutrition Foundation, Fuse: the Centre for Translational Research in Public Health and The Association for the Study of Obesity.


Adapted with thanks to Food Active


Image: 'primary school, lunch, break, school, activities' by Amanda Mills, USCDCP via PIXNIO (https://pixnio.com/people/children-kids/primary-school-taking-their-daily-lunch-break-during-their-school-day-activities) (Personal & commercial use (CC0).

Friday, 6 March 2020

Out of the shadows: Corporate activity and our health

Posted by Nason Maani, Harkness Fellow, Boston University School of Public Health

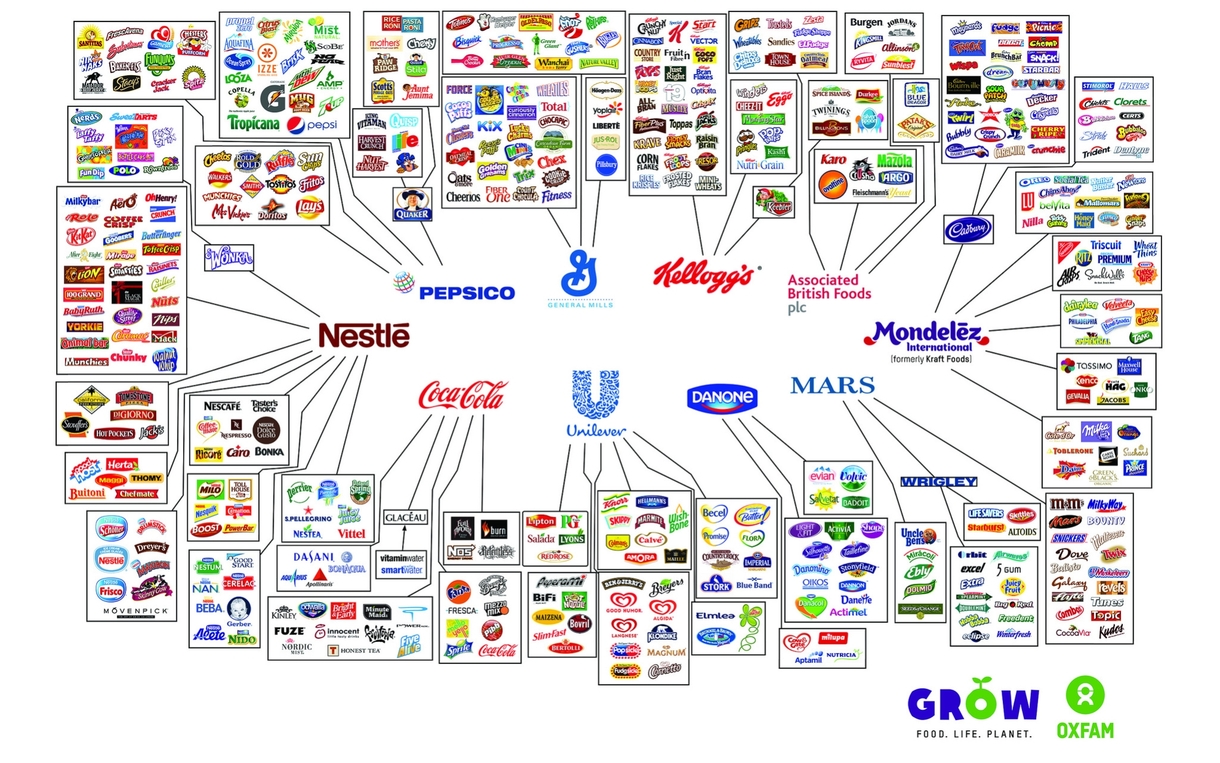
When considering the impact of commercial actors on health, our minds in public health turn immediately to tobacco. However, while the tobacco industry has earned its reputation and associated exclusion from policymaking, what is unique about those actors misleading policymakers and the public for commercial advantage? Arguably, nothing at all. Asbestos, leaded paint, fossil fuel, sugar-sweetened-beverage and alcohol companies and their proxies have been found to pursue similar tactics.

This is not to say that large commercial actors cannot in many cases benefit society while making a profit. Rather, it is to say that such commercial actors have a track record of focusing on maintaining profit while avoiding litigation, negative PR, and regulatory burdens. When these goals conflict with population health, such actors have the power and scale to negatively influence health, the evidence base, policy options, and even public discourse. The commercial determinants of health, in their broadest sense, are defined as activities of the private sector that affect the health of the population.

As we discussed in a recent commentary, there is a need to progress our understanding in this area because all these areas of influence matter to societal progress, and there are commonalities across many different industries in terms of their motivations, strategies, networks, tactics and interventions that merit the attention of public health researchers.

There is also currently a lack of conceptual focus on these powerful actors by policy-makers and non-governmental organisations, and some gaps in our thinking about these issues. We know that it is largely the conditions in which we are born, grow, live, work and age that determine our health, sometimes called “the social determinants of health”. However, in a recent review, we showed that commercial determinants were often absent from conceptual frameworks of the social determinants of health. This is problematic because such actors have the incentives, resources and strategic ability to influence everything from individual behaviours, attitudes and preferences, to the pollution of the environment, and the funding of politicians who are unwilling to consider the weight of evidence on a particular issue.

Oxfam’s infographic making the connections between big companies and some very familiar brands.


There is a large space for study in this area, but many challenges to doing so, not least because there is relatively little research funding or political will to tackle these issues directly. Many researchers and advocates remain “silo-ed”, focusing on a particular product, or discipline. This “zoomed-in” view stands in contrast to the intersectional ways in which a single large company might act, never mind an industry sector as a whole, or different industry sectors with overlapping interests, acting, for example, to diminish employment rights or environmental standards. We argue that there must be much greater scope for the convening of interdisciplinary research to explore these issues and offer potential solutions.

What about practice?

Aside from research, what about practice? There is also a need for the evidence that does exist to translate more effectively into policy. The challenge public health practitioners often face is that there is a strong political will for partnership and collaboration with the private sector at the local, national and global level, both through direct partnerships, and multilateral engagements. Such arrangements are, on the face of it, appealing. Access to the resources of the private sector is an obvious solution to the problem of increasingly restricted budgets for public health departments, particularly as these private resource pools are so large. Voluntary commitments between the public and private sectors are also conceptually appealing, echoing the type of multi-stakeholder engagement that public health advocates strive for.

However, in the UK, the evidence suggests such activities are often characterised by an abundance of words (in the form of voluntary pledges) and a paucity of deeds (in the form of meaningful changes to how harmful products are produced and marketed). Without regulatory safeguards, it appears unlikely that harmful product manufacturers will voluntarily act in ways that could reduce their own profit margins or lead to “stranded assets”. Instead, such actors will go to great lengths in framing themselves as part of the solution to a “complex” problem, while attempting to diminish the role they play in creating that problem, and rejecting what they termed “one size fits all” approaches such as policy best buys.

There is, however, progress on the research front. Research on specific harmful products and the industries that produce and market them continue apace, and commonalities in corporate strategies are being increasingly discussed. Networks of interested researchers in related topics are beginning to emerge. Perhaps most promisingly, it is becoming clear that commercial determinants are an important component of the broader determinants of health. As the “elephants in the room” become more widely perceived in issues such as alcohol harm, climate change and the opioid crisis, let us hope that, informed by a growing evidence base, the tools to properly address them will follow.


Photo attribution:
  1. "140/365 - Coke Shadow" by Adam Wyles via Flickr.com, copyright © 2011: https://www.flickr.com/photos/the-travelling-bum/5418900013 (CC BY-ND 2.0).
  2. Oxfam infographic courtesy of Oxfam, copyright © 2013: https://firstperson.oxfamamerica.org/2013/03/10-everyday-food-brands-and-the-few-giant-companies-that-own-them

Friday, 21 February 2020

Workplace Health and the Cauldron of Evidence

Scott Lloyd and Sarah Slater, Advanced Public Health Practitioners, Public Health South Tees 

Systematic reviews are brilliant. They take all the available evidence for a particular topic, do something special (stick the results into a big cauldron) and churn out a finding that informs us mere mortals in policy and practice where we should and shouldn’t be investing our money and capacity.

Double, double toil and trouble...
In these austere times, such evidence about what works and what doesn’t is so important – especially when combined with the how and why. This recent review by Jenna Panter and colleagues is an excellent example of what works and how.

However, there is one sphere of public health where we feel that systematic reviews may not paint a full and fair picture.

Let us explain.

Workplace Health


Most public health colleagues have a speciality or five. This might be a topic (e.g. nutrition or addiction) or part of the life-course (e.g. children and young people or older adults).

We are Workplace Health Specialists with 28 years of combined experience. We’ve supported employers of all descriptions, including businesses of different sizes and in different sectors. We’ve worked on national workplace health programmes, such as the Well@Work programme led by the British Heart Foundation between 2005 and 2007, and have been involved in the North East Better Health at Work Award since its launch in 2009 (arguably the biggest and most successful workplace health programme in England). We’ve a lot of experience of supporting NHS organisations who are trying to improve the health of staff – sometimes successfully, sometimes less so.

Working with such a variety of employers to improve staff health is a challenge of both knowledge and skill because they are looking to you, as the expert, to come up with evidence-based suggestions. Consider how you might support the below employers (real examples for us) to encourage physical activity in their workforce:
  • A tea factory which operates 24 hours a day with mixed shifts and a predominantly female, part-time workforce
  • A call centre for a bank employing 1,200 mostly young staff, in a mainly sedentary occupation
  • A call centre for a public sector organisation employing workers typically aged 40 plus, in a mainly sedentary occupation
  • A mining company at which the majority of the workforce arrive, take a lift down a shaft for 20 minutes, work a shift underground in 40 degree heat, resurface in the lift and get straight in the car to head home
  • A category B prison. 
How would you support an employer to encourage physical activity in a call centre?
What you might suggest to each of the above five employers (and what might work) could be completely different (and probably would be). At least in each of those scenarios, the workforce is likely to be pretty homogenous. Consider working with a huge employer such as a Local Authority or NHS Trust which arguably have massive internal differences in staffing groups in terms of age, gender, hours, and roles (e.g. office staff vs refuse collectors).

We believe that these differences make workplace health a different kettle of fish compared to other settings, such as schools, colleges, universities, and prisons, which could be comparatively homogeneous. They aren’t of course – there are massive differences between schools for example, but our suggestion is that they have the potential to be very similar if all variable things (e.g. culture, policies etc.) were the same. 

What’s our point?

Firstly, that lumping trials of workplace health interventions and programmes into a systematic review masks these potentially huge differences. We’re not sure how we get around this issue but we are raising it as an issue.

Secondly, to suggest that there is a lot more research to be done. There are some workplaces that should be considered a priority. For example, the majority of the working population in the private sector (60%) are employed by small-to-medium sized enterprises (less than 250 employees) and this is an area that no-one has cracked in terms of health and wellbeing via the workplace. Another example is call centres: given the sedentary, pressured nature of the work. One feasibility trial has recently been completed (Morris et al. 2019)[1] and another is underway (involving Scott). We can’t do individual studies for every type of workplace but some should be considered a priority.

Thirdly, to highlight the skills possessed by our peers who lead on workplace health. Employers and employees can throw all sorts of issues at you from bread and [low fat] butter stuff like physical activity and mental wellbeing to stuff like menopause awareness and sleep. Not only does a workplace health specialist need to maintain a base knowledge of all these topics, but they also need to understand how it might be tackled in the various types of workplace highlighted above.

It would be remiss of us not to plug the North East Better Health at Work Award. It needs a stronger evaluation building on previous work (Braun et al. 2014)[2], but we’re talking about a programme that was launched in 2009 and has actively engaged hundreds of employers every single year since (456 currently engaged at January 2020), supporting them to promote the health and wellbeing of their staff (potential combined reach of 202,962 working adults as of January 2020) and the wider community. We’re always recruiting more businesses so if you would like to know more visit www.betterhealthatworkne.org.


References
  1. Morris, A.S., Murphy, R.C., Shepherd, S.O., Healy, G.N., Edwardson, C.L. & Graves, L.E.F. (2019). A multi-component intervention to sit less and move more in a contact centre setting: a feasibility study. BMC Public Health, 19 (1), 292                                    https://bmcpublichealth.biomedcentral.com/articles/10.1186/s12889-019-6615-6
  2. Braun, T., Bambra, C., Booth, M., Adetayo, K. & Milne, E. (2014). Better health at work? An evaluation of the effects and cost–benefits of a structured workplace health improvement programme in reducing sickness absence. Journal of Public Health, 37 (1), 138 –142  https://academic.oup.com/jpubhealth/article/37/1/138/1559494


Image 2: Photo by Arlington Research on Unsplash

Friday, 14 February 2020

Uniting planning and health to tackle obesity

Public Heath England (PHE) has just published practical guidance, informed by Fuse research, for local authorities wanting to use the planning system to improve public health. In this blog post Andy Netherton and Michael Chang, from PHE's Healthy Places Team, tell us how they hope the guidance will be used to tackle obesity.


Obesity is a modern day public health challenge that cannot be met by a traditional scientific approach alone. Tackling obesity levels in England requires action by national and local government, health and social care, non-governmental agencies, communities and individuals – a whole system approach.

Traditionally the vast majority of public discussion and state campaigns target individual level behaviour change and treatment. This does not address the environment in which we live, that influences the decisions and actions that we make; things such as what we eat, whether we exercise, how we travel to work, how we interact within the community and if we have access to and use open spaces.

These physical environmental factors can be influenced by national and local policy and action. State led interventions are difficult to put into place due to the need for evidence within complex social and environmental determinants. The difficulty to isolate evidence related to these interventions and local government capacity to balance competing demands results in an inconsistent approach to policy adoption.

The use of planning policy and development management is a clear example of an intervention to tackle obesity which is not yet consistently applied across the country. Practice across the country has shown a diverse range of approaches in local plans and planning appeal decisions which has taken over 10 years to develop, but is now accelerating.

Figure 1 – Charting the use of planning for healthy weight environments


This policy to implementation lag has to be seen in the context of an increasing obesity challenge, both in terms of prevalence and health inequalities.

Figure 2 – key obesity data and trends

Statistics on Obesity, Physical Activity and Diet, England, May 2019 - NHS Digital, Government Statistical Service


Is the reason down to the nature of local evidence provided or the knowledge of the individual local authority teams, planning inspectors or the wider planning regime?

This was recognised within the Childhood Obesity: a plan for action, Chapter 2. The challenges it identified, included the proliferation of fast food outlets, less active travel, limited access to green spaces and physical activity; and these factors create an environment that makes it harder for children and their families to make healthy choices, particularly in some of our most deprived areas.

The Childhood Obesity plan confirmed that local authorities have a key role in tackling this challenge and pledged support:
  • to make sure that all local authorities are empowered and confident in finding what works for them, and;
  • to develop resources that support local authorities who want to use their powers and provide up to date guidance and training for planning inspectors. 
In response Public Health England (PHE) has released guidance on using the planning system to promote healthy weight environments.

Previous research by PHE (Spatial Planning and Health: Getting Research into Practice (GRIP) study report) identified that local authorities would benefit from support that reduced the need for resource input, for example reduced duplication to create policy and practice. This publication is aimed at getting knowledge into action by providing guidance and a template supplementary planning document (SPD), one of many planning levers available to local authorities, that can be used by local authority planning and public health teams. It answers the following questions:
  • What is the current evidence base linking the built and natural environment and healthy weight? Specifically, can the local food environment influence diet and obesity?
  • How can the planning regime be used to promote healthy weight environments?
The publication identifies the background work necessary in order to comply with planning policy development, where the key is the use of local evidence and consultation. It specifically provides guidance on the use of the 400m exclusion zone for hot food takeaways, features of the built environment and building design that promotes physical activity, use of green space, allotments and neighbourhood design.

The provided supplementary planning document (SPD) is a starting point that requires local content and policy to be added. It can be used as a whole or parts selected on local need or to dovetail to existing local policies. Clearly this intervention is one intervention that must be used within a wider national and local obesity strategy.

There remain challenges to promoting a healthy food environment, for example the impact from the rise of industrial kitchens for food delivery must be monitored. Work must continue to influence the energy and compositional content of other food options and build our homes and neighbourhood to allow people to more active.

This publication provides guidance on a practical evidence based intervention that draws together several professional groups within a local authority. Gateshead Council have successfully adopted and defended on appeal, controls on hot food takeaways as part of a wider approach to tackling obesity and promoting healthy weight environments. It is hoped that for many areas working together to tackle obesity will provide confidence to further unite planning and health. It moves the debate from a deficit model of obesity to an asset based (salutatogenic*) approach to promoting healthy weight.


*Israeli-American sociologist Aaron Antonovsky coined the term "salutogenesis" to describe an approach which focuses on a positive view of wellbeing rather than a negative view of disease.

Wednesday, 5 February 2020

Coronavirus: expect the unexpected in an unfolding emergency

Posted by John Mooney, FFPH (Fellow, Faculty of Public Health), Fuse Associate & Senior Lecturer in Public Health at University of Sunderland @StandupforPHlth 

In an age when public health and health improvement efforts in much of the world are justifiably focused on chronic disease, lifestyle factors and the ever increasing health and social care needs of an ageing population, we would do well to remember that humankinds’ most determined and persistent adversaries are always “waiting in the wings” ready to step on the stage for a lead role once again.


Step forward new variant Coronavirus (2019-nCoV), which the World Health Organisation has declared a Global public health emergency[1] reminding us all of the enduring critical importance of basic public health principles and practice and internationally co-ordinated vigilance for new microbial challenges. ‘International’ of course being a critical component of any response plans, since infectious diseases do not respect national borders and less so, referendum results. The first confirmed UK cases on Friday[2], currently being treated in this region, only serves to remind us of the ‘global village’ we all inhabit from the perspective of infectious diseases.

Coronaviruses are a large family of viruses, some causing (mostly mild) illnesses in people and others that circulate among animals, including camels, cats and bats. The recently emerged 2019-nCoV is not the same as the coronaviruses that caused Middle East Respiratory Syndrome (MERS) or Severe Acute Respiratory Syndrome (SARS) though genetic analyses so far suggests that the new variant is more closely related to SARS[3].

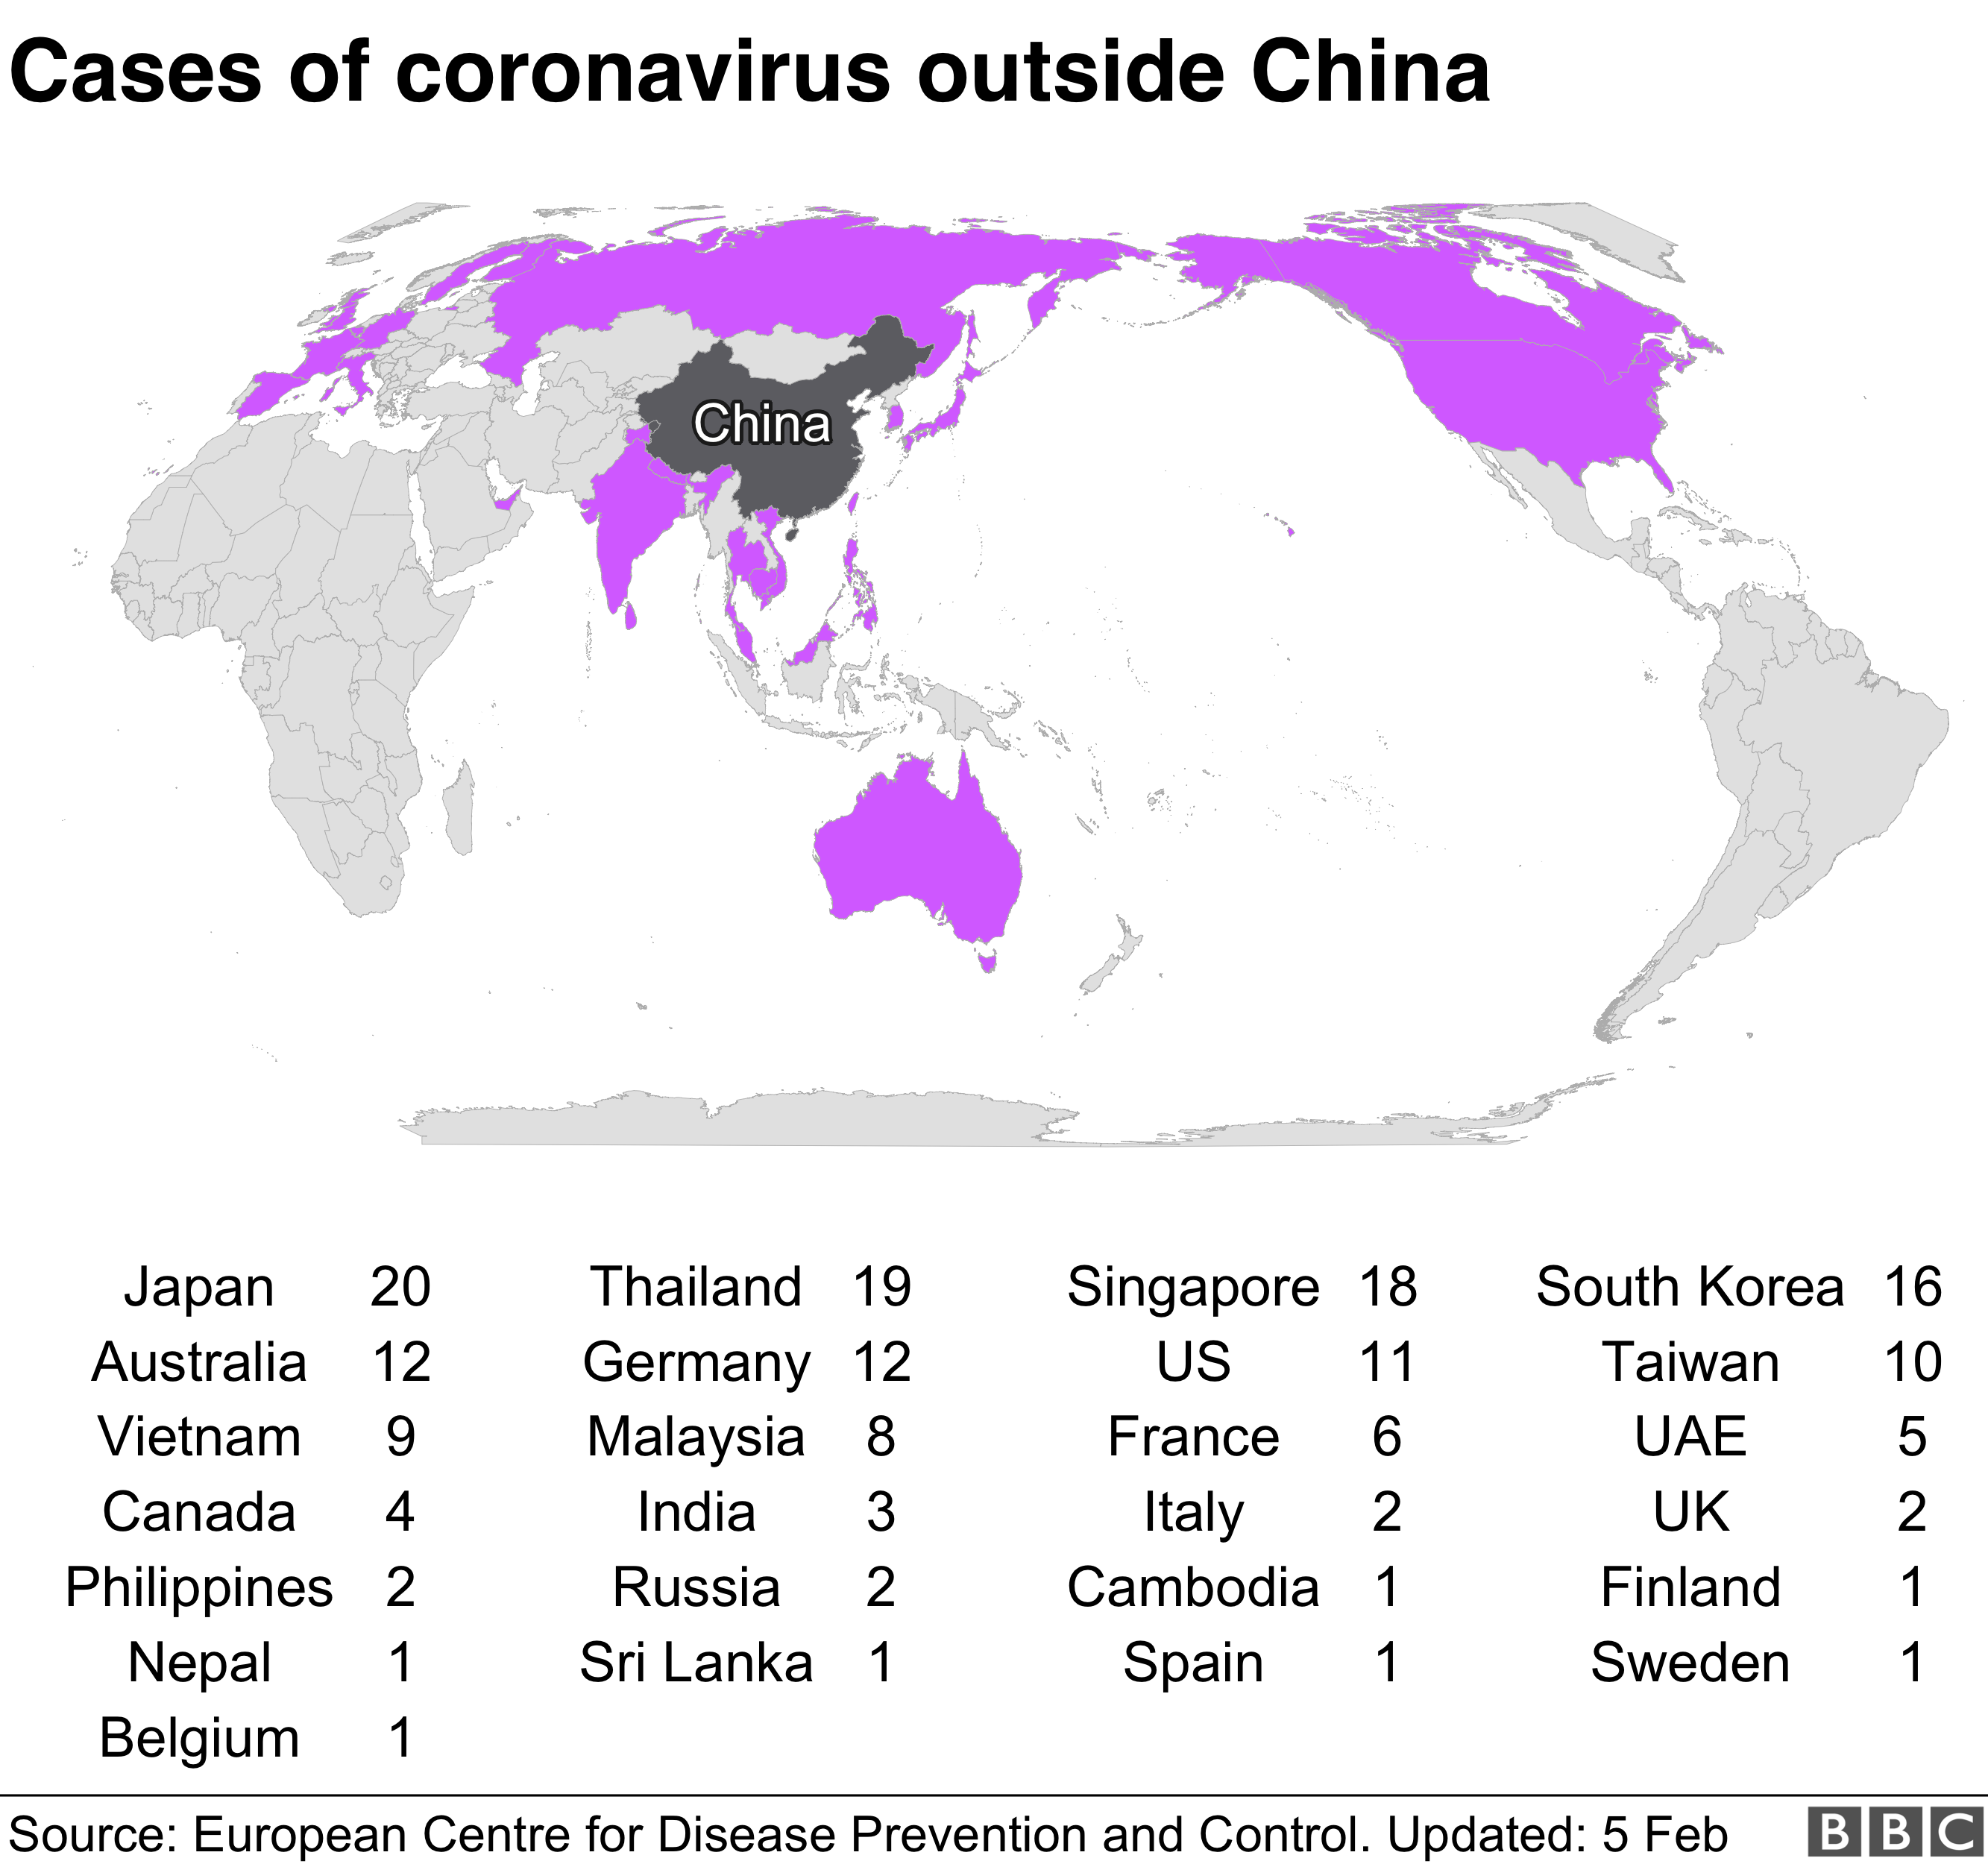
Ninety Nine percent (99%) of the 24,000+ cases and nearly all of the 490 confirmed deaths (with 2 exceptions, one in Hong Kong and one in the Philippines) so far have been in China.  Despite this, the WHO emergency declaration crucially allows for additional resources and support for lower and middle-income countries to strengthen their disease surveillance and prepare them for potential cases or outbreaks. At the present time, to the considerable credit of the Chinese response – partly arising of course from international condemnation of a less than transparent response to the SARS outbreak in 2003 – there are Herculean efforts and resources being devoted to containing the threat from the new pathogen.  This includes the drastic attempted quarantine of a whole region and the speed of construction of new facilities such as 1000 bed dedicated hospitals.


While 2019-nCoV seems to be less lethal than SARS, there is no doubt that it is clearly more transmissible with The World Health Organization stating that the preliminary R0 (reproduction number) estimate is 1.4 to 2.5, meaning that every person infected can potentially infect between 1.4 and 2.5 people (R0 for SARS being 0.19–1.08, with a median of 0.49)[4]. With the spectrum of clinical presentations ranging from mild respiratory illness to life threatening viral pneumonia, the health impact of the ongoing outbreak is very difficult to predict and unanswered questions abound. How many people may have shrugged off mild / virtually asymptomatic infections for instance is not possible to know until follow-up sero-conversion studies[5] can be used to estimate the burden of ‘silent infections’.

Aside from higher transmissibility, the more worrying aspect of 2019-nCov however is the reports of an incubation period of up to 14 days during which an infected individual might both be asymptomatic (displaying no evident symptoms that could be screened for) and also crucially, at the same time during this period, infectious and capable of transmitting the virus to new hosts. The potential 14 day incubation period without symptoms effectively means that the cases which are being confirmed at the present time merely reflect the ‘true burden of infection’ from two weeks ago. As a result we will only have any real sense of the effectiveness of Chinese efforts to contain the virus a fortnight after the stringent travel restrictions imposed around Wuhan province and other parts of China.

As many seasoned experts in these matters have cautioned, schooled as they have been by experience of previous episodes, predicting the behaviour of a newly emergent pathogen is a hazardous business and a great deal of uncertainty surrounds its likely route to potential pandemic status. A virus adapting to a new species host (in this case humans!) is an unstable entity and its defining characteristics today in terms of those who are most vulnerable and their risk of serious or life threatening illness may be very different in the weeks and months ahead.

Eventually of course, a virus keen on longevity in a new host needs to curb its pathogenicity[6] and ideally result in only mild symptoms that will reduce the attention it attracts from a host immune response. Many of the hundreds of viruses, including coronavirus subtypes that cause the common cold, once jumped the species barrier and evolved into relatively benign pathogens. Even the deadly “Spanish flu” epidemic of 1918[7], which killed around 60 million people Worldwide in 1918-1920 and comprised of the influenza subunits H1N1, circulates today in the form of seasonal flu in a genetic variant with greatly reduced lethality.

How serious the current outbreak will be in terms of impact and mortality remains to be seen. SARS of course was eventually successfully contained by stringent infection control, contact tracing and quarantine procedures. While 2019-nCov is not currently as life-threatening an illness as SARS, its greater transmissibility, longer incubation period and potential for symptomless transmission (SARS was only transmissible when symptomatic), do not bode well for ease of containment so it is hardly surprising that the WHO have seen fit to play their strongest card and declare it an emergency.

We can only hope that the response may be timely enough.


John Mooney worked previously for NHS Health Protection where he specialised in the epidemiology of respiratory infectious diseases.


References:
  1. Coronavirus declared global health emergency by WHO: https://www.bbc.co.uk/news/world-51318246
  2. Coronavirus: UK patient is University of York student: https://www.bbc.co.uk/news/health-51337400 
  3. 2019 Novel Coronavirus Basics: CDC FAQs: https://www.cdc.gov/coronavirus/2019-ncov/faq.html
  4. Emerg Infect Dis. 2004 Jul; 10(7): 1258–1263 https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3323341/
  5. Seroconversion: The development of detectable antibodies in the blood that are directed against an infectious agent. Antibodies do not usually develop until some time after the initial exposure to the agent.
  6. Pathogenicity is defined as the absolute ability of an infectious agent to cause disease/damage in a host - an infectious agent is either pathogenic or not. From: Fenner and White's Medical Virology (Fifth Edition), 2017
  7. 1918 Pandemic (H1N1 virus): https://www.cdc.gov/flu/pandemic-resources/1918-pandemic-h1n1.html

Image 2: Capture from the BBC News website, 5 February 2020. Coronavirus: Ten passengers on cruise ship test positive for virus. Source: European Centre for Disease Prevention and Control. Updated 5 Feb. https://www.bbc.co.uk/news/world-asia-51381594.

Friday, 31 January 2020

Does reaching the ‘hard-to-reach’ mean leaving traditional academia at the door?

Angela Wearn, PhD Researcher, Department of Psychology, Northumbria University

“You tend to find the ones that are protesting and telling you to go and get your smears are the ones that have their cushy little jobs and that lovely flash car that they can just jump in and dive down to the doctors”


From all the conversations I’ve had throughout my research career, this is one of the quotes that has stuck with me the most. For over three years I have been working on my doctoral research, conducted across Newcastle, which explores barriers to cervical screening participation in areas of high relative deprivation. We know that uptake rates tend to be lower in areas of socioeconomic disadvantage, but reviewing existing literature showed very little insight from women who lived within these communities themselves. Incidentally, I am one of these women. I grew up, and still live, within a neighbourhood which, according to the Index of Multiple Deprivation, falls within the 10% most deprived areas in the country. It’s therefore no accident that I ended up with a programme of research which aimed to prioritise the voice of this community.

Graffiti walls can be a simple and effective way of starting conversations
Initially, I had dreams of a wonderfully participatory project, where I formed a steering group and we worked together to find answers and seek solutions. As often happens in research, time ticked on and it didn’t work out the way I had planned. My participatory ideals had to take a backseat for a less time-consuming participant-researcher approach. I suspected my ‘insider’ status might open doors for me and to be fair, it did. I found myself being able to quickly connect and build a rapport with others when I discussed my own background and why I wanted to do this project. However, getting to the point of even having these conversations was by no means easy. I spent days, weeks, months trying to speak to community groups, charities and community members about my research. Some were very open and interested, others were not. I attended community get-togethers handing out cakes alongside research information, making ‘graffiti walls’ with post-its, even chatting about life over freshly made biryani at a cookery club. Actually, these were the most rewarding and enjoyable moments over the past three years, but the more I did this the more I felt I was straying from what academia expected of me. I also began to feel my status as an academic researcher was a hindrance to what I was aiming to do at community level. For a lone PhD researcher, bringing together these two worlds, at times, felt completely impossible.

"community get-togethers...were the most rewarding and enjoyable moments over the past three years, but the more I did this the more I felt I was straying from what academia expected of me"

Attending community events was a great way to connect with 
people who were otherwise unfamiliar with research
The quote at the beginning of this blog was when it all clicked into place. Although we were talking about cervical screening, I acknowledged something that I had already known all along - the same issues of accessibility and trust apply to involvement with academic research. If I put my working-class hat on for a minute, academic research feels neither accessible nor promotes interpersonal trust. From the outside, academia appears to be filled with people who think they know better than you, patronising you, sometimes even using you to showcase the poor decisions people make in life. I had to work hard to reassure people that I wasn’t there to pass judgement on their screening status. I’m still not sure many believed me. ‘Eat a healthy diet’, ‘Stop smoking’, ‘Engage in physical activity’, ‘Attend your screening appointments’. These are the messages that come through, focusing on the individual and discounting all the structural and social barriers that exist for people living in communities like mine. If you are trying to figure out how to afford the weekly food shop, the kids have come home with a tear in the coat you only bought a fortnight ago and you’re worried about not getting enough work from your zero hours contract, there is no mental space for ‘living your best life’ (and certainly no space for sitting with a stranger from some university taking part in a research study).

Those living in socioeconomically disadvantaged areas are often described as ‘hard-to-reach’. This often implies that despite best efforts to reach out, these groups are disinterested and disengaged. I tend to believe the reverse is true. Some groups are hard to reach because academic research is too disengaged from the community. I know of many academics who are so obviously committed to tackling the avoidable and unjust disparities in health, and for this reason I do feel positive for the future. However, as someone who is positioned in between the ivory towers of academia and the working-class neighbourhoods at home, I know there is still a lot of work to do. There is a long history of mistrust and marginalisation to put right. If we are serious about tackling inequality and involving so called ‘hard-to-reach’ groups in research, then we need more focus on developing trust and togetherness…and occasionally, this might mean leaving traditional academia at the door.

Friday, 24 January 2020

Is Exercise Referral fit for a new decade?

Posted by Coral Hanson, Emily Oliver, Caroline Dodd-Reynolds and Paul Kelly

“Exercise referral doesn’t work”. We have heard this said time and time again, particularly by those who are peripherally aware of the field, but perhaps most worryingly by commissioners and those involved in public health policy. We’ve argued that this is simply not true. A different interpretation is that the exercise referral evidence-base, and the way it is used, hasn’t been working.

The term ‘exercise’ conjures images of Mr Motivator-style aerobics in eye-searing 1990’s lycra


Exercise referral is a decades-old process where professionals in primary care (GP/practice nurse) or secondary care (specialist doctor/physiotherapist) refer patients to a community-based physical activity scheme - often delivered by a leisure provider. National policy guidance (NICE, 2014) recommends that referrals are made where a patient is otherwise inactive or sedentary (both different parameters and not simple to classify in a primary care setting such as a GP surgery) and additionally has an existing health condition, or is at risk of having one.

Traditional evidence-generation for exercise referral has tended to be single-site studies that are then condensed using systematic-review-based methods. Given the considerable variation in how schemes are designed, delivered and evaluated at local level, this is problematic. Vague policy guidance and limited evaluation funding means that most scheme iterations are unsuitable for inclusion and interpretation in this outcome-driven way (Oliver et al., 2016). Collectively, the findings of such overviews are rather underwhelming.

Consequently, during times of tightened public health spending and commissioning, many UK exercise referral schemes have been de-commissioned. This seems misguided, given evidence that some schemes work, for some individuals, in some contexts. Understanding these nuances is at odds with the ‘best practice’ and ‘scaling-up’ that is so often seen as desirable within physical activity policy. Evidence must (and thankfully is starting to) account for consideration of local tailoring and best fit for a given community. Incorporating such evidence into policy is a different matter, of course.

To assist with collating evidence that can meaningfully inform policy and commissioning decisions in this area, our recent editorial in the British Journal of Sports Medicine proposes a sea change in how exercise referral is considered, categorised and reported. The term ‘exercise referral’ is outdated in 2020. ‘Physical activity referral schemes’ more appropriately describes the innovative and extensive range of programmes being delivered, and allows for other types of referral including self-referral, social prescribing and group-based needs assessments, to potentially contribute to the evidence base.
Personally, we’re not keen on the term ‘exercise’; it conjures images of Mr Motivator-style aerobics in eye-searing 1990’s Lycra. It sounds so imposed and constrained
You may have noticed we have replaced ‘exercise’ with ‘physical activity’ – surely a more inclusive term for what is ultimately a behaviour – and one which we are trying to change. Traditionally exercise referral schemes were mainly gym-based and we think that this image probably persists when we think of exercise referral today. Personally, we’re not keen on the term ‘exercise’; it conjures images of Mr Motivator-style aerobics in eye-searing 1990’s lycra. It sounds so imposed and constrained. Even a simple phrasing change can have far-reaching implications, and hopefully for the better in this case.

In the editorial, we propose a simple way of identifying, classifying, and recording key information about physical activity referral schemes that will enable better understanding of what exists and what is working. Our new reporting checklist (or taxonomy) encompasses all physical activity schemes that:
  1. have the primary aim of increasing physical activity,
  2. have a formalised referral process, 
  3. are provided for individuals who are inactive/sedentary, and/or have or are at risk of a health condition. 
The classification framework can be seen in figure 1 (below). The full reporting checklist can be found in the editorial. We propose that this be used by commissioners, practitioners and researchers alike: for auditing and monitoring, to capture service delivery and in generation of evidence reviews.

Figure 1
We are very keen to hear from anyone working in exercise/physical activity referral of any kind as we move forward with refining this idea. The model was proposed to policy-makers, practitioners and academics at a consensus event in late 2019, and we are currently refining it by undertaking a Delphi Survey. We are inviting further comment, critique and engagement to make the final version as accessible and ‘fit for purpose’ as it possibly can be, so please get in touch with Coral, Caroline, Paul, or Emily via twitter or email - details below.


Coral Hanson, Research Fellow, Edinburgh Napier University @HansonCoral / C.Hanson@napier.ac.uk

Emily Oliver, Associate Professor, Director of Research in the Department of Sport and Exercise Sciences, Durham University @_EJOliver

Caroline Dodd-Reynolds, Associate Professor, Department of Sport and Exercise Sciences, Durham University @carolinedod / caroline.dodd-reynolds@durham.ac.uk  

Paul Kelly, Lecturer in Physical Activity for Health, The University of Edinburgh @narrowboat_paul 


References:

Images: 
  1. Mr Motivator 2’ by Dave Tett via Flickr. Attribution-NonCommercial-NoDerivs 2.0 Generic (CC BY-NC-ND 2.0): https://www.flickr.com/photos/66551670@N00/388434590 © 2007.
  2. 'Figure 1' reproduced from Hanson, CL, Oliver, EJ, Dodd-Reynolds, CJ & Kelly, P (2019). We are failing to improve the evidence base for “Exercise Referral” How a PhysicalActivity Referral Scheme Taxonomy can help. British Journal of Sports Medicine Published Online First: 17 December 2019. doi: 10.1136/bjsports-2019-101485 with permission from BMJ Publishing Group Ltd.

Friday, 17 January 2020

School food research and teenage diets mean sleepless nights and a mountain to climb

Posted by Kelly Rose, Graduate Tutor/PhD researcher at Teesside University

In the spirit of the commencement of the New Year, I thought it the perfect timing to write a second Fuse blog post reflecting on my first year of PhD study. Also, driven by my waking at 2am, Monday of the first week back in a cold sweat, realising I am more baffled than ever!

In my first blog post, I described myself as feeling at the bottom of a mountain…

Now a year and a half in, I can report some relief at successfully passing my annual review, confirmation that I have the capability. This is definite progress, and a sure sign of having climbed at least a little higher towards the summit. A few days ago I also celebrated my 44th birthday, and I suppose the coinciding of a new decade brought a significantly reflective mood (in the most positive sense). This past year has tested me in so many ways that I had never expected. If you want to know yourself at a deeper level, I think a PhD certainly would be the recommendation. I started this journey with the attitude (that I was always telling my students and children) that anyone can do anything they set their mind to. This mantra has definitely helped in times of significant self-doubt.

Progress update

So far, I have completed a systematic review, had a paper of the political timeline of food policy published in the Nutrition Bulletin, shared my research in a conference, and was boosted by an article I contributed to the conversation.com being shared in the Independent online.

What have I learned?

I left secondary school teaching in July 2018 with a strong sense that more was needed to improve adolescent nutrition. Today, with more of a grasp on the research, I am even more incredulous as to why more is not being done by policymakers.

The evidence is clear, teenagers have the poorest diets of any other age group in the UK. The Lancet commission stated we can reap huge benefits from improved health policies, focusing on the global adolescent population, after all they are our future parents and workforce. As I found in the political timeline research and systematic review, there are many examples of good practice with regards to implementing and evaluation of school food standards, whole school policy and health interventions. But still no priority being placed on consistent evaluation and of policing school food provision in England.

Waking up at 2am questions
  • Why is our school food provision failing to improve adolescent nutrition?
  • Why does the Childhood obesity strategy (part 2) make the assumption that all schools in England are following the national school food standards when there is no evidence that most schools are? #pizzaandcookies. 
  • Why the inertia and lack of prioritising teen diets, when the evidence points to the impacts of diet on mental health and school performance? 
Of course, it’s just not that easy, because, this is a multilevel issue, and the problem is much more complex than just implementing a policy or three. There are significant barriers to challenge, as we see the commercial determinants to health as a major part (defined as “strategies and approaches used by the private sector to promote products and choices that are detrimental to health” (Kickbusch et al 2016)).

One of the factors I want to focus in on over the next two years, is the social aspect of teen diets. It is becoming more and more an accepted ‘norm’ that teenagers have a poor diet, and food choice is a major factor in fitting in with peers, with healthy food choices often ridiculed. A low risk perception of unhealthful food choice seems to be a barrier in improving the health of the next generation. I wonder how we can flip this influence.

With all the reflecting done, I am ready to move forward into 2020. This year the plan is to see my systematic review published, to plan and conduct research in building a picture of experiences, views and what is happening in a range of schools in the North East. And with this public declaration I aim to keep momentum and to contribute to the body of research moving forward.

Keep believing and achieving.


Image:
"Junk fast Food illustrations infographics editorial" by Svajune Garnyte is licensed under CC BY-NC 4.0

Friday, 10 January 2020

Now that's what I call blogging 2019

Posted by Mark Welford, Fuse Communications Officer, Teesside University

Happy New Year – can I still say that or have we reached peak-greet when this obligatory salutation is no longer required in email, phone, or awkward fleeting corridor exchange?

This time of year is all about numbers: the 12 days of Christmas, the pounds you’ve gained (lbs) or lost (£), counting steps, units, the 31 days of Dry January, Veganuary, or the point at which you can grant yourself a run free day.

It therefore seems fitting that the Fuse blog has a countdown of its own.  Last year was a fine vintage for blog posts but you may not have had the opportunity to read all 40 of them.  To save you time we have had a look back and created a Top 5 Chart of the ‘bestsellers’.

So without further ado, here’s our chart toppers:

5. The provocatively titled Can cancer ever be a good thing? in which Fiona Menger (@slt_fi) revisits the writing of 'cancer columnist' John Diamond while working on a head-and-neck cancer research study with a focus on a phenomenon called post-traumatic growth.

Page views: 585.  Posted: 31 May 2019 

4. In What old crisp packets dig up Duika Burges Watson (@debedub) gets hands on to unpack the mystery of the humble crisp.  What is their continued value as ‘food’ and can we still enjoy them as a cultural icon without creating so much waste and damaging our health?

Page views: 640.  Posted: 22 February 2019

Still from the animation
3. Why do some women continue to smoke when they are pregnant?  Sue Jones (@Susan_E_Jones) shares research findings on overcoming barriers to implementing NICE guidance on supporting pregnant women to quit smoking.  The blog includes a short animation which was developed based on the findings.

Page views: 663.  Posted: 10 May 2019

2. If at first you don’t succeed, try, try, try & try again...  Suzanne Moffatt (@SuzanneMoffatt) reflects on 58 months of knock backs in her efforts to secure ‘the big grant’ because multiple failures before success is often untold and sometimes persistence pays off.

Page views: 686.  Posted: 15 February 2019

Courtesy of Children's Future Food Inquiry via twitter
1. "It’s time to act!  It’s time this country gave every child the right to food!"  Pamela Graham (@PamLGraham) begins her blog post with this powerful statement from Corey (pictured right), a 15-year-old Young Food Ambassador who sat on a stage in Westminster and bravely told an audience about her experiences of food insecurity.  With more than double the views of its nearest competitor, Young people taking a stand for their #Right2Food takes the crown as most popular blog post in 2019.

Page views: 1474.  Posted: 03 May 2019

So there you have it, the top five Fuse blog posts from 2019. Can we can do any better in 2020? If you fancy giving it a go, please find out what we are looking for and how to take part here.


P.s. perhaps we need to look more closely at what's going on in February and May!?


Image:
  1.  'Now That's What I Call Music! 1989' by brett jordan via Flickr. Attribution 2.0 Generic (CC BY 2.0): https://www.flickr.com/photos/x1brett/45056607035/

Friday, 20 December 2019

Happy New Year from everyone at Fuse

We would like to wish all our readers and contributors a very Happy New Year - why not make a resolution to blog in 2020 and send us your posts?


Image (adapted with thanks):
The original uploader was Rsabbatini at English Wikipedia. [CC BY 4.0], via Wikimedia Commons.

Tuesday, 3 December 2019

Scaling the mini Matterhorn - risk and adventure with a disability

Posted by Llinos JehuResearch Associate with AskFuse, Teesside University

Llinos introducing the blog and speaking about her experience of epilepsy

Happy ‘International Day of Persons with Disabilities’! That day set aside by the United Nations to ‘promote the rights and well-being of persons with disabilities in all spheres of society’.

There’s a lot to be happy about. When I was diagnosed with epilepsy in the 1970’s, the world was a very different place. I got used to being treated as a fire and safety hazard (so not allowed into some buildings or events), a risk (so refused insurance), and a liability (excluded from school trips ‘just in case’). Given all the gloom and doom, it’s amazing that I turned out to be such a boringly average sort of person, never knowingly causing anything to spontaneously combust.

Roseberry Topping has been compared to the Matterhorn in the Swiss-Italian Alps
And generally I am happy living as someone with epilepsy, identifying as a disabled person. But then I attend something like the launch of the NIHR Applied Research Collaboration (ARC) in North East & North Cumbria, and get told that I’m going to die 10 years before everyone else. OK, they didn’t actually say that, they didn’t necessarily mean me. But people living with a disability or long term condition are at risk of premature mortality, and that risk isn’t always linked with their condition. For me, good epilepsy management is dependent on taking medication like clockwork. Seizures don’t stop me from taking my medication, but having to remember to order a repeat prescription just might: not more than 10 working days before I run out, but not less than 8 working days as it takes time to process. Good epilepsy management requires a good standard of physical and mental health: managing the weight-gain that the medication can cause, managing stress and anxiety, getting a good night’s sleep. Most people want to achieve some of the things on that list. Epilepsy doesn’t stop me from travelling with my job or going out to see friends; that’s caused by poor public transport. Unless I actually drop down with a seizure (and there’s no reason that I should), epilepsy won’t stop me from doing a 16 mile hike across the Moors. Barriers are more likely to be caused by people asking me, ‘Are you sure you should? Is it safe? Is it wise?’.

Speaking to Steph Kilinc about her research on the experiences of people living with adult-onset epilepsy

So what would make me happy, and possibly live a bit longer? Good, accessible, affordable public transport for starters. And a text from my pharmacist to say that my meds are ready to collect – after all, they know I’m a responsible person who takes them as instructed. They also know I’m not the sort of person who will stock-pile meds to sell on the internet or feed to my goldfish! The text wouldn’t just make sure I had the meds to take, it would make an enormous contribution to reducing levels of stress and anxiety. It would make me feel that I was viewed as an adult with a range of competing demands on my attention, rather than an old child with nothing else to think about.

Phil and Llinos on how technology helps them to navigate both walks and public transport

What already makes me happy is that I’ve had a life filled with friends who’ve supported and encouraged me. They’ve helped to keep the stress and anxiety levels down, to get the good night’s sleep, to manage the risks and have the adventures. There’s still lots to be unhappy about. Sometimes I’m really, really angry. Hate crime targetting disabled people, increasing levels of inequality: sometimes there can seem little to celebrate. But for this year’s event I’ve walked up Roseberry Topping on a glorious day, accompanied by two great friends: Phil Jeffries who’s a very experienced walker and happens to be partially sighted, and Steph Kilinc, a member of Teesside University’s Behaviour, Health and Resilience Research Group who happens to be a somewhat less experienced walker. We’ve compared Steph’s research findings with our own experiences of living with a disability. Phil’s shown how technology can help someone with a visual impairment to read maps (actually how to interpret maps, he was good at orienteering before his sight loss and there’s only so much technology can achieve). Together we’ve managed to navigate the public transport system and arrived at the same place and at the same time. I’m not stressed, I’m not anxious, I’ll take my meds and have a good night’s sleep. I’ll leave being angry until tomorrow, when I might follow up on those ARC presentations and find out what’s to be done to address that premature mortality risk.


References:
  • Stephanie Kılınç a,. The experience of living with adult-onset epilepsy, Kilinc S, van Wersch A, Campbell C, Guy A, Epilepsy & Behvious 73 (2017) 189-196
  • Thomas R & Barnes M, 2010, Life expectancy for people with disabilities NEUROREHABILITATION Volume: 27 Issue: 2 Pages: 201-209