Friday, 9 April 2021

Feeling like an imposter? Learn to get comfortable with ambiguity

Peter van der Graaf, Fuse Knowledge Exchange Broker, Teesside University and Travis Sztainert, Knowledge Mobilization Specialist, Frayme

Do you ever feel like your lack of ability or knowledge is going to be exposed? In that case, you might suffer from Imposter Syndrome! Knowledge Mobilisers work across boundaries and are asked to perform tasks that they don’t feel “qualified” for, triggering feelings of anxiety and failure. What causes these feelings and how can we overcome them? In an attempt to answer these questions, we compared experiences across the pond by reflecting on our roles as Knowledge Mobilisers in Canada and in the UK. We argue that these feelings should not be avoided but harnessed by turning imposter syndrome into a useful repertoire for the role.

"Piled Higher and Deeper" by Jorge Cham www.phdcomics.com


In March the annual UK Knowledge Mobilisation Forum took place, which brings together practitioners, researchers, students, administrators and public representatives who are engaged in the art and science of sharing knowledge and ensuring that it can be used. This year, the Forum was held online for the first time, and one of the sessions was dedicated to interactive posters. Participants could preview posters in GoogleDocs and leave comments and questions for the presenters, who were later interviewed to respond to the feedback left on their posters.

In our poster, we explored why Knowledge Mobilisers are particularly prone to feelings of being an imposter. They work in a competitive specialist profession; everyone strives to be a guru, but at the same time their work occurs in the background. It often goes unrecognised if done well (and shows up particularly bad if it fails!) but is time-intensive with work often being unclear, making it feel like you’re not moving forward.

Our poster - see the full version here


Developing trusting relationships between knowledge producers and users often requires complex and lengthy conversations, which only increase the risk of being exposed as an imposter. At the same, there are limits to collaboration (not everybody wants to work together or share their knowledge), which can add to feelings of failing at your job as a knowledge broker.

Moreover, the role requires you to be a neo-generalist with varied expertise and, therefore, there is always more to learn. Organisational change and consequently personal change (the one certainty of working in the health and care sector) are always on the horizon, meaning that you have to continuously adapt your role. In addition, system changes often change the knowledge and evidence that is required by users and this increases transaction costs (time and resources spent on adapting knowledge) for boundary workers.

However, there is a lack of ‘professionalisation’ of the field and training is scattered: this can make you feel like you’re missing essential skills and knowledge. During the poster session we conducted a quick poll to ask how many participants had received formal training in knowledge mobilisation: 83% had not. Or as one of the participants summarised: Knowledge Mobilisation is a Cinderella service. Being undervalued by funders, universities and professional organisations means you are often faced with a lack of resources and unable to do your job. In fact, it is often expected that Knowledge Mobilisation can be done “off the side of the desk” or in addition to work as a researcher or policy maker. Thus, a paucity of time and space is set aside to adequately tackle complex issues.

To overcome these challenges, the first rule of Knowledge Mobilisation is that you need to be comfortable with ambiguity. Feeling like an imposter is not (in itself) bad, is a normal part of the learning process, and can be harnessed. Skills are most often developed on-the-job, and feelings of imposter syndrome can help drive you to learn more, do better, and be open to new concepts and experiences. Overconfidence can lead to a lack of insight into your weaknesses, which in turn can lead to actually becoming an imposter. Accept that you have shortcomings and areas for improvement. It’s okay not to know what you’re doing, or not to have all the answers. Think of yourself as an enthusiastic learner who is gaining experience and expertise - imposter syndrome will help you to stay humble.

Being open and honest about not having all the answers can actually be seen as a strength. As one participant pointed out in response to the poster: it helps to level power differences between partners by showing that you don't hold all the power (and are human like everyone else) and therefore empowers those working with you. It's ok for them not to know it all too and therefore may prompt questions that people may otherwise have been afraid to ask, leading to more open conversations, and strengthening relationships and trust. It can also mean that, when you are sure of answers, others know that they can trust you because you have previously shown that you would not say you knew something when you did not.


Participants described this as a cyclical process, where feelings of imposter syndrome drive new learning, which increases your confidence to go into new situations that lead to fresh experiences of imposter syndrome, starting the cycle again. Forum members also emphasised the importance of operating as a team: the vast amount of skills required as a Knowledge Mobiliser (keynote speaker Annette Boaz mentioned connectivity, charm, inclusivity, empathy, creativity, integrity, curiosity, diplomacy and humility for starters), means it is almost impossible to develop these skills as an individual. Teams of Knowledge Mobilisers can bring these skills together and use different skills at the same time.

Moreover, acting like an imposter can be a valuable role: by communicating out of character a knowledge broker can help to make sense of differences in knowledge use. Adapting to the audience and stage required helps knowledge brokers to translate differences in performances between policymakers, practitioners and academics. Knowledge Mobilisers should not fear being an imposter but instead learn to embrace imposter syndrome!


If you are interested in learning more about imposter syndrome in knowledge mobilisation, take a look at:

Friday, 2 April 2021

Working together to tackle inequalities and inactivity

Posted by Sophie Phillips, Fuse & NIHR School for Public health Research (SPHR) funded PhD Researcher, Department of Sport and Exercise Sciences, Durham University, and Dr Rachel Mowbray, Insight Coordinator, County Durham Sport, Active Partnership.

In today's Fuse blog post, Sophie and Rachel tell us about collaborating during Sophie's secondment at County Durham Sport between January and March 2021.

It seems obvious that we would work together, right?

I conduct research in an academic institution and Rachel promotes evidence-based working in an Active Partnership which collaborates closely with Durham County Council. Our day-to-day roles are quite different. But, we have a shared goal: to tackle inequalities that stand in the way of physical activity engagement and support children and adults to be more active. By working together, combining knowledge, skills, and connections, we think we can make even greater progress towards improving people’s health and wellbeing.

How is academic research positioned within the physical activity landscape?

Physical activity policy and practice is a large and complex system made up of many different organisations, approaches, and settings. Academia is often positioned as external to the system, trying to create impact from the outside through activities referred to as ‘pathways to impact’. But in reality, academic research could be a crucially important element of the system in its own right (but often doesn’t have that position). Can positioning academic research as part of the system (as opposed to outside the system) make creating impact less of a hurdle and more of an opportunity?

Through my secondment to County Durham Sport, academic research has been embedded into the local Active Partnership. This gave me a huge opportunity to make an impact (on a daily basis!) by simply talking to others in different parts of the system. By sharing my knowledge and passion through conversations, I felt like I could make a real difference. Sharing information and ideas can challenge and influence thinking. This can (and does) influence the way things are done.

What are the benefits of an embedded researcher in policy or practice?

Rachel:
Non-academic audiences often cannot access academic publications in meaningful ways because of financial barriers and/or because of the academic format. Having Sophie embedded in our organisation brought academic research to life and into the conversations happening between practitioners, policy makers, and non-academic researchers. These conversations allowed us to access the most up-to-date and robust information about physical activity. In the same way, County Durham Sport were able to offer extensive knowledge of the local physical activity system and inequalities. Working together, we created a stronger evidence-base on which to tackle the challenge of inactivity.
Sophie: I was able to communicate knowledge from academic research papers on physical activity into meaningful insight for County Durham Sport. One of the pieces of work I conducted during the secondment was a report on early years physical activity and movement. This included translating evidence from academic research papers into meaningful and accessible outputs (including reports, overviews in tables, and presentations). I was also able to engage with different stakeholders and physical activity providers across multiple settings, who are involved with local early years provision. This helped to bring together both the research evidence and the current local landscape, to make evidence-based and actionable recommendations about future early years provision.

Take-home messages from our collaborative experience…

Our day-to-day roles are very different, as are the expectations and outcomes of our work. Although this presents some challenges (such as differing timescales and required outputs), ultimately, we share a goal - to tackle inequalities that stand in the way of physical activity engagement, support everyone to be more active, and help to improve people’s health and wellbeing. Finding this common ground can foster true collaborative thinking and drive connections between academic and non-academic players in the physical activity system. Integrating our different perspectives and approaches is beneficial and necessary to create meaningful system change.

Rachel: Tackling big issues (like inequalities in physical activity) requires a collaborative and evidence-based approach. I would encourage other third sector organisations to engage directly with academic researchers - both to learn from their expertise, and to share your own experience of practice or policy. We can achieve more working together than we can alone!

Sophie: My experience of collaboration with County Durham Sport has been invaluable. It has influenced the way I think about conducting and communicating research. I would encourage other public health research PhD students to explore the opportunities of engaging in a short time with policy and practice partners in their field, to help view their work from different angles.


Sophie’s academic research is about measuring the physical activity and movement behaviours of pre-school aged children. Her secondment at County Durham Sport was funded by UK Research and Innovation (UKRI) QR Strategic Priorities Fund awarded through Durham University.

Rachel promotes evidence-based partnership working to tackle inequalities in physical activity through her role with County Durham Sport, Active Partnership funded by Sport England.


Images:

2 & 3. Photo of Rachel (https://www.countydurhamsport.com/about-us/meet-the-team) and Sophie (https://www.countydurhamsport.com/homepage/news/) with thanks to County Durham Sport.

Friday, 19 March 2021

Simple, likeable, luck? How to get physical activity research into practice

Posted by Nicola McCullogh, Post-graduate Researcher, Northumbria University

Sometime last year – I can’t remember exactly when due to lockdown blur – I was asked by my mentor Caroline Dodd-Reynolds if I’d like to join the Fuse Physical Activity Network. I’d been to a number of workshops and I loved the focus on putting knowledge into practice, so I said yes and spent the rest of the year being in awe of the speakers we’ve had from across the world. And the discussion following the first workshop of 2021 (22nd January) was so rich that we wanted to do a bit of a follow-up to – as they say – ‘continue the conversation’.

                                     Watch a recording the 5th Fuse Physical Activity Workshop

This isn’t a report on the workshop itself, but it would be wrong to start on the discussion between the attendees without first acknowledging the speakers who inspired that discussion. First Professor Adrian Bauman (University of Sydney) spoke about how we can improve physical activity practices locally and nationally, and then Ben Rigby (Durham University) took us through 10 guiding principles for local physical activity practice which were developed by the Fuse Physical Activity Network. Some of the points that jumped out from the chat box during the presentations were around the topics of:
  • Inclusivity: How can we make sure that physical activity messages get to specific groups of people? (e.g. can we do this via carers?)
  • Scalability: Physical activity interventions tend to be less effective when scaled up; is this because they are often adapted in the scaling-up process?
  • ‘Business as usual’: Should we move away from thinking about physical activity programmes and towards encouraging physical activity by integrating it into people’s daily lives?
  • Making every contact count: How can we measure the effects of conversations between health professionals and patients about regular physical activity in a way that meets the definition of ‘evidence’ for all of the different groups interested in this sort of practice and research?
As you can see, there was so much going on that it’s no surprise there were a few things we didn’t get to explore on the day! So we pulled together the remaining key themes from the chat and these are considered below.


Are physical activity interventions long enough, as it can take years to become active/inactive? And when we’re researching interventions do we give enough thought to people staying active afterwards?

This seems to be one of those areas where there’s an unfortunate disconnect between research and practice. At the workshop we discussed the value of academic research in understanding the needs of communities but also acknowledged the potentially lengthy timeframes involved before research hits policy and practice. On the other hand, limitations on the practice side can include timescales over which practitioners need to deliver interventions due to funding requirements, meaning that interventions may be shorter than they would ideally be. When it comes to people staying active, although studies with follow-ups do exist, interventions tend to try to give their participants the skills to stay active on their own once the programme finishes, rather than being ‘maintenance interventions’. Maybe we need to try an approach a bit like weight loss groups for ongoing support?


Could we use financial incentives to increase people’s physical activity?


Anyone who knows me knows I love a bit of self-determination theory so I’m going to default to that for my answer, though of course other theories are available! Tying in with the above question, I think what we all want to see is interventions with long-term effects. Financial incentives might encourage physical activity while incentives are available, but we’re unfortunately not giving people the motivation to continue without these rewards and we know the rewards won’t last forever. On another level, those running the interventions have targets to reach to show the effects of their work, so they’re operating under short-term reward systems, too. Shifting our targets towards long-term effects may help.


How can we address the social factors that influence physical activity?


Social determinants of health (conditions in which people are born, grow, work, live, and age) are well recognised by physical activity researchers and practitioners. On a broad level, interventions try to reduce anything that would hinder participation for the groups they aim to help. But an interesting area of thought is how we can use people’s sense of belonging to a group, and their perception of what that group does, to encourage them to be active (e.g. encouraging new parents to be active together at parent and baby groups). We just need to explore the best ways to do this when people identify with groups to different degrees and their group identifications can change over time.


Our efforts can be supported by following the 10 guiding principles for local physical activity practice, which bring together some of the issues discussed above including social determinants of health, inclusivity, and harnessing things that are already happening to promote physical activity. Over the years there have been many different initiatives to encourage people to get active, and some of them have really stuck. The Daily Mile is a simple idea to get children moving in schools, and it seems to be something that works for pupils and staff because it’s been running for over five years now. And Park Run has been successful around the world for over a decade. So it might seem like it’s difficult to get something in place that has an effect, that is sustainable and that people actually like, but sometimes with a bit of luck we can put research into practice and it all comes together.

I think the overall conclusion – summarised very nicely by Professor Bauman – was "keep trying".

What do you think? Let us know in the comments below.


Thank you to everyone who attended the webinar and contributed to the discussion, and to everyone involved in the Fuse Physical Activity Network for their support.

Wednesday, 10 March 2021

Should pregnancy 'be incentive enough' to quit smoking?

Guest post by Susan Jones, Research Associate, Teesside University

I have seen many people on twitter express the view that thinking about their baby should make pregnant women automatically quit smoking. Indeed many women when they decide to try for a baby or find out they are pregnant do quit smoking. However, it does seem illogical - and shocking - to many that this is not always the case.
 

For those who do continue to smoke, it is perhaps more of a hint of a complex web of reasons behind their smoking behaviour, rather than any greater willingness to harm their baby. Smoking throughout pregnancy is often associated with environmental and social deprivation, which gives us a clue. Hilary Graham’s seminal work into women’s smoking and its association with family health, published in 1987, opened the door to a new understanding of what some of the reasons might be for this apparently illogical and paradoxical behaviour on the part of pregnant women from deprived communities. Graham concluded that:
"The study suggests that, for a significant minority of mothers, poverty and caring combine with low levels of physical and emotional energy, with sleep problems and with feelings of social isolation. In this context, smoking appeared to provide a way of coping with caring-in-poverty: a way of coping alone with the demands of full-time caring and with the struggle of making ends meet."
This work revealed that there were other, stronger reasons to continue smoking, which counteracted any impulse to quit.

Guilt and shame

An earlier study of ours heard pregnant smokers confess to feeling guilty and ashamed of smoking in pregnancy and how they are very aware of the stigma associated with their behaviour:
“But then once I lit it up and had half of it I felt guilty. But it took that edge away, but I still felt guilty. So if I felt even more guilty I probably mebbees wouldn’t have touched it, but I feel weak because I have had to do it.”

“I think the kids always make it like, they have more effect on you than what anyone else does, because they're, well you feel guilty if you're letting them down and doing something they don't want you to do.”
We also found that sometimes it can be a distrust of public health messages combined with a real lack of knowledge about the mechanics of how smoking affects the developing baby. Nevertheless, it must be acknowledged that, for whatever reason, not everyone says they want to quit; but of those who do want to quit, some say they do not feel able to. For the sceptics out there, this may seem only subtly different to choosing to smoke, alternatively it may be a real barrier to quitting. Graham’s work would suggest the latter. More recent research has built on her findings and investigated what methods of support may work for these pregnant women, who do not quit, and for whom the health outcomes are comparatively worse for themselves and their babies.

What can be done?

Research over several decades has shown that there are ways to support pregnant women to quit smoking, focusing on:
  • Referring to stop smoking support services
  • Offering support to change behaviour
  • Support through medication.
It is clear now that opt-out approaches to referral and carbon monoxide monitoring and much more personalised support are also helpful to women (see our short video below).


Work has been undertaken to implement these supports more fully; e.g. the Local Maternity Systems (LMS) in North East England designed the Maternity Pathway and have led the work across the organisational systems to integrate these mechanisms. Becca Scott, the North East Local Maternity Systems Public Health Prevention Lead says:
"The LMS have led North East organisations and service users to contribute to the target of 5% or less women smoking in pregnancy by 2025. That would mean 2723 fewer women smoking at time of delivery across the North East since 2018. It does this by offering all expectant mothers, and their partners, a multiagency-developed, smoke-free pregnancy pathway and minimum service standards (as detailed in each of the Maternity providers bespoke plans). The impact of the engagement with the work has seen prioritisation throughout all Local Authority Health and Wellbeing boards, as well as consistency in the way smoking in pregnancy is identified and supported, which is demonstrated in significant improvement in adherence to NICE Guidance."
What more can be done?

The results of this partnership work are encouraging. Is there anything else that can be done? The evidence for the effectiveness and cost-effectiveness of financial incentives to support pregnant women to quit has been building. Trials have been conducted which have found that there is "substantial evidence for the efficacy of incentives for smoking cessation in pregnancy" – however this idea has encountered significant public scepticism and opposition.

ash. Smoking in Pregnancy Challenge Group Webinar - Incentive schemes


Although there has been more balanced reporting too and more recently, the headline below suggests the idea has become more acceptable.

Capture from The Sun online (09/03/21)

Modelling financial incentives in smoking in pregnancy

A team of us (details below*) have been awarded funding from the NIHR Applied Research Collaboration (ARC) North East & North Cumbria Open Funding Competition to look into an alternative way to take into account the views and responses from all stakeholders, including staff, pregnant women, and the public. We will also be building a mathematical model based on Evolutionary Game Theory (EGT). EGT is a mathematical framework of contests, strategies and analytics into which Darwinian evolution can be modelled. It is designed to capture the strategic interactions between stakeholders, because ultimately these interactions will drive health behaviour. Incentivisation will be modelled to see how it affects some behaviours and in what contexts. We hope the model will be able to guide commissioning and provision, so that any intervention is as effective and cost-effective as possible, without having to conduct further lengthy and expensive trials beforehand. Watch this space!


*Associate Professor Emma Giles (Teesside University), Professor Falko Sniehotta (Newcastle University and University of Twente), Dr Jean Adams (University of Cambridge) and other partners working in NHS Trusts and local authorities. Colleagues in the School of Computing, Design and Digital Technologies, Associate Professor The Anh Han and Tedy Cimpeanu from Teesside University.

Friday, 5 March 2021

Patient and Public involvement with Parents during a Pandemic: the four ‘P’ challenge

Posted by Hannah Batten, Food and Human Nutrition undergraduate student, Newcastle University.  Hannah is on a placement year with the Population Health Sciences Institute, as part of the MapMe intervention team.

If you have a primary school age child, then you’ve probably heard of the National Child Measurement Programme (NCMP). For 13 years, it has collected data on the height and weight of children aged 4-5 and 10-11 years old in England. This information is used to calculate what is called the ‘weight status’ of a child and the results reported to parents via letter. Unfortunately, these letters often receive a mixed response, with many parents mistrusting the results.

Research has also shown that parents often struggle to recognise if their child is overweight, preventing them from taking action to address this.
Body image scales on the MapMe website are currently being updated for MapMe2


This issue sparked the development of the MapMe intervention, led by Fuse Director Prof Ashley Adamson and Angela Jones, which aims to help parents assess child overweight / obesity. The MapMe tool includes:
  • sex and age specific body images of children ranging from underweight to very overweight
  • information on the consequences of being overweight in childhood
  • advice on healthy eating, physical activity and links to further support.
Funded for large scale testing by the National Institute for Health Research, the MapMe tool will be delivered as part of the National Child Measurement Programme across nine areas, aiming to improve how parents respond to the letters and the NCMP process, supporting parents to take action.

The project originally had a 3-year time frame, with the intervention scheduled to be delivered in 2020/21. But, as with many other things, COVID-19 got in the way and with schools closed this prevented the delivery of the NCMP, which delayed the project by a year. Although this was disappointing, it has allowed extra time for us to focus on preparing for the next part of the study focusing on Patient and Public Involvement (PPI).

Doing PPI during a pandemic

PPI involves gaining insight during the research process from members of the public, improving research by providing additional expertise from a non-researcher perspective. One key task for the MapMe2 study was to figure out how we could recruit and run an online Parent Involvement Panel (PIP) to help review documents and study materials, when parents are already dealing with a global pandemic.

Recruitment and communication

To accommodate people being stuck at home during COVID-19, parents were recruited through social media and network sites such as the Newcastle University staff pages. Once the Panel was created, we asked parents how they wanted us to communicate with them and kept in frequent contact via email and newsletter to keep them informed and engaged in the project. As this was unknown territory for everyone, good communication with the Parent Involvement Panel was essential.

Moving online

Pre COVID-19, we had planned to hold face-to-face meetings with the parents in easily accessible venues such as the Great North Museum in Newcastle upon Tyne. However, as has become the norm with lockdown and social distancing measures, in person gatherings have been replaced with Zoom meetings. On the plus side, this allowed the meetings to go ahead and parents to attend from any location, but did result in frequent technical issues! When preparing for remote meetings, we sent out documents to parents in advance and scheduled breaks to avoid ‘Zoom fatigue’. We also used ice breakers at the beginning of sessions to make parents feel at ease.

Making information accessible to all

COVID-19 has intensified the digital divide in the UK, with a large number of people having limited access to, or understanding of, devices. Reading information and training documents on the small screen of a smartphone or tablet is not a practical or enjoyable experience. In an attempt to address this, we send hard copies of the Parent Involvement Panel manual through the post.

We have also created videos that will be posted on YouTube (example below), making them easily accessible to parents whenever they wish. The videos include members of the study team welcoming and informing parents about the project and their role, as well as short animations providing training tips. Although these are perhaps not Oscar-winning performances, they provide the information in an alternative and accessible format for volunteers.


Learning from our experience in carrying out remote Patient and Public Involvement during COVID-19, information needs to be provided in an accessible way like videos, and volunteers need to be aware and comfortable with the options available to feedback their opinions.

Saying thank you

Finally, and most importantly, is to say to our participants that we are extremely grateful for their time and input, particularly during these uncertain times.

As long as we are mindful of these new challenges, online Patient and Public involvement can still be a valuable and effective way to work.


Part of our Fuse blog Student Series
The Fuse blog Student Series showcases posts by students who have been challenged to write a blog as part of their studies at one of the universities in the Fuse collaboration, the NIHR School for Public Health Research, or perhaps further afield. The authors may be new to blogging and we hope to provide a 'safe space' for the students to explore their subject and find their voice in the world of public health research.

Friday, 26 February 2021

Four practical steps to increase knowledge exchange between researchers and policymakers

Posted by Peter van der Graaf, NIHR Knowledge Mobilisation Research Fellow, Teesside University

Are you keen to have impact with your research but get lost in all the knowledge exchange frameworks and models that are out there? In this blog, Peter calls upon 10 years’ experience working in translational public health for Fuse to identify four practical steps to develop collaborative research and achieve meaningful change in policy and practice.


We know all about the challenges of using research to inform policy and practice, especially in public health where the evidence base for interventions or programmes is patchy or contested. In response to these challenges, countless models and frameworks have been developed that try to define the knowledge exchange process (how research evidence can be used, in combination with other types of knowledge, to change policy and practice). Practitioners and researchers venturing into the field of knowledge exchange can be bewildered by the options available which don’t go beyond concepts and fail to describe in practical terms what research translation looks like in reality.

Here I want to share practical guidance from our research on ‘how to do’ knowledge exchange by reflecting on a model that has been developed in Fuse over the last ten years. Our approach to achieving practice and policy change has been to engage with practitioners, policymakers and the public through communications and knowledge brokerage, to co-create relevant research, influence policy and practice debates and promote evidence uptake. Below I have broken this down into four practical steps:
  • Step 1. Awareness raising: Making evidence users, funders and support organisations aware of our existence, our research and engagement opportunities, including engaging our partners early in setting the agenda for future research.
  • Step 2. Sharing knowledge: Creating opportunities for research users and producers to come together to explore opportunities for mutual learning and knowledge exchange through collaborative events, our responsive research service (AskFuse), and patient and public involvement.
  • Step 3. Making evidence fit for purpose: Localising and tailoring evidence to context by offering a knowledge brokering service, embedded research, and increasing awareness of the different pressures faced by people in health policy, practice and academia.
  • Step 4. Supporting uptake and implementation of evidence: Developing long-term relationships with policy and practice partners to co-create evidence, build capacity for practice change, and change practice and policy.

It is important to link a range of knowledge exchange activities that engage policymakers and practitioners at different levels, intensities and points in their decision-making and development processes.

For example, before meeting with policy and practice partners, we develop tailored research briefs that summarise study findings in an accessible and visual way, and that emphasise recommendations and implications for policy and practice. Involving Fuse researchers in developing these briefs improves their knowledge exchange skills, while providing them with ‘calling cards’ to initiate relationships with policymakers for further collaborative work. These conversations are often followed by requests to AskFuse on how knowledge users can apply the research evidence in a specific context, invitations to engage in collaborative research, or to support capacity building and implementation.

Knowledge exchange between academia and public health practitioners and policymakers can be complicated and at times bewildering. Breaking the process down into practical steps illustrates that knowledge exchange is empirical and relational.

Friday, 19 February 2021

"Whatever their answer, double it and you should be close..."

Posted by Hannah Mehmood, Medical Student, Newcastle University

Hannah undertook a 6-week NIHR School for Public Health Research (SPHR) internship with Fuse based at Newcastle University in summer 2020. She was supervised by Fuse / NIHR SPHR Doctoral Student, Cassey Muir.

A question asked in every GP consultation is how much alcohol a patient drinks. It provides a useful insight into a person’s physical, social, and psychological health. According to my GP tutor, most people underestimate the amount they drink, as well as the impact this has on them.

Substance misuse is a complex issue, and as a medical student I have learned to focus on the impact of problematic drug and alcohol use on individual patient wellbeing. Last summer, as an NIHR SPHR intern, I studied substance misuse from a different perspective. The basis of my internship was a research project focusing on young people whose parents misuse drugs and alcohol. I aimed to explore how young people viewed school and education to understand if this environment could be used to deliver supportive interventions.

I analysed ten UK based qualitative studies which examined the experiences of young people affected by parental substance misuse. Qualitative studies examine non-statistical data to develop themes and deep understanding of the research question. The young people from the studies I explored were under the age of 25 and from various social, economic and demographic groups.

Young people viewed school as a space away
 from issues they may face at home
I was particularly interested in the ways in which young people viewed school as a separate space away from issues they may face at home, to the extent that many young people did not even discuss their home life with close friends. But despite the mental separation of home and school, the reality of their home life often prevented a complete detachment of the two. One young person described how caring for her parent resulted in frequently missing school, while another recognised that his aggressive behaviour in school was a way to offload stress at home.

Many young people also expressed a lack of trust towards their place of education, as well as a desire to blend-in with their peers. This contributes to barriers in identifying young people who may benefit from intervention, as many are fearful of being singled out while in the detached school environment.

In conducting my research, I came to appreciate the difficulty in generating themes from such varied experiences. I often felt that my insights did not do justice to the nuances of each individual story. I discussed this in a virtual meeting with a programme coordinator at ADFAM, a national charity that works with families affected by drugs and alcohol. Her experience, delivering interventions at an operational level, allowed me to see how my research fit into the real world. I came to understand that while research is conducted with the aim of applying findings to whole populations, these findings are only actionable when combined with existing knowledge and expertise. This discussion was a lesson in the value of cross-collaboration, an important tool in bridging the gap between research and intervention.

Over six weeks I have broadened my understanding of public health, conducted my own research project, developed my professional skills, and furthered my personal career goals. Although this internship took place remotely, my mentors enabled me to virtually meet various public health professionals. Hearing about their research roles, motivation and future plans has shown me the variety of career paths available within public health and helped to develop my own ambitions. The NIHR SPHR internship with Fuse has been a valuable personal and professional experience and I would recommend it to other students interested in pursuing a career in public health.


Part of our Fuse blog Student Series
The Fuse blog Student Series showcases posts by students who have been challenged to write a blog as part of their studies at one of the universities in the Fuse collaboration, the NIHR School for Public Health Research, or perhaps further afield. The authors may be new to blogging and we hope to provide a 'safe space' for the students to explore their subject and find their voice in the world of public health research.


Images:

1. 'Doctor with prescription stop drinking alcohol' by Marco Verch Professional Photographer via Flickr.com, copyright © 2019 (Attribution 2.0 Generic (CC BY 2.0)): https://m.flickr.com/photos/30478819@N08/48719845996

3. Logo courtesy of ADFAM https://twitter.com/AdfamUK/photo

Friday, 12 February 2021

Placement, parcels and a pandemic: five weeks embedded in a public health team

Posted by Maisie Rowland, Research Assistant and Registered Nutritionist, Human Nutrition Research Centre (HNRC), Newcastle University

Newcastle Civic Centre
My research has taken me from primary schools in the West End of Newcastle to rural schools in the mountains of Moshi, Tanzania but I have always been curious about other job roles and what they involve. I have also been interested in how, as researchers, we can collaborate with those outside of academia to ensure that the research we do has the desired impact. So on seeing an advertisement for an embedded researcher placement in Newcastle City Council with the Public Health team, I put in an application. This felt like a great opportunity to expand my knowledge of other job sectors, while creating links outside the university and maintaining my work in the HNRC (working there one day a week). Before I knew it, I was walking to the city’s Civic Centre for the first day of my five-week placement.

I spent my first week learning about the wide variety of projects and roles the team were involved in, such as the redevelopment of Fenham library to include a drugs and alcohol recovery hub and the health education with schools and young people. I was able to sit-in on a number of interesting meetings and was able to contribute to the Wider Determinants of Health team meetings. I learned about how projects happen and was surprised at how much it differed from a university research setting, such as the different resources used for background research for projects and the differences in terms of ethical approvals. I was also given the opportunity to put forward my ideas and interests and, working alongside my colleagues Dr Annette Payne (Health Improvement Practitioner) and Lorna Smith (Speciality Registrar in Public Health), we developed an idea for a project working with food banks. As a nutritionist, I have a strong interest in this area. Through conducting online research, and visiting food banks and ‘pay as your feel’ supermarkets, we gained an insight into how these organisations and similar providers work. We also learned about the nutritional content of ‘standard’ emergency food parcels, the demographics of those who find themselves needing to use food banks, the situations these people might be in, and finally the shocking numbers of people finding themselves in need of using them. From this research, we developed a report which was presented at the Public Health Senior Management Team meeting for approval and feedback from other team members. Our project was well received, which was encouraging, and we were given the go-ahead to continue with our work.

Life Foodbank in Newcastle upon Tyne
From this background research, I learned that those who use food banks have usually been referred through care providers (such as through school or through social workers), and there is a limit on the number of times they are able to use the food bank. Help is given in the form of an emergency food parcel containing at least three days’ worth of food, and users are often offered help and advice which aims to resolve the issues that have led them there. Although there has been nutritional guidance on the food parcels, the reality is that a lot of the food comes from public donations. Therefore, as the donations vary, so will the food parcels. Within the team, we considered possible changes to the parcels that could be suggested, in order to benefit those who have to use food banks. It was quickly decided that any work we did would be with the food banks themselves, rather than those using the food bank. We devised a plan with three ‘phases’, including:
  • Phase one involved a consideration of how to suggest very small changes to the ‘food call outs’. For example, typical foods that are given in food parcels, and are regularly requested in the call outs, include breakfast cereals, soups, pasta and pasta sauces, rice, tins (beans, meat, vegetables, and fruit), tea or coffee, sugar, biscuits, snacks, jams, and fruit juice. Due to the variation in these particular food groups, and the variation in the foods that are donated to the banks, the nutrient content of the packages will also vary widely. Our suggested changes to the call outs will include requesting tinned fruit in juice rather than syrup, reduced sugar/salt baked beans and tinned pasta in sauce, tinned vegetables without added salt or sugar, and higher fibre/lower sugar breakfast cereals.
  • Phases two and three will involve creating some user-led resources for the food banks such as recipe cards, which will provide inspiration for different meals that could be made from the foods in the parcels. We also hope to include a ‘community access card’, which will provide information on nutrition, healthy weight ranges and local support available. The local support would involve signposting to free cooking classes, food banks and ‘pay as you feel’ supermarkets, community groups, and computer facilities at libraries.
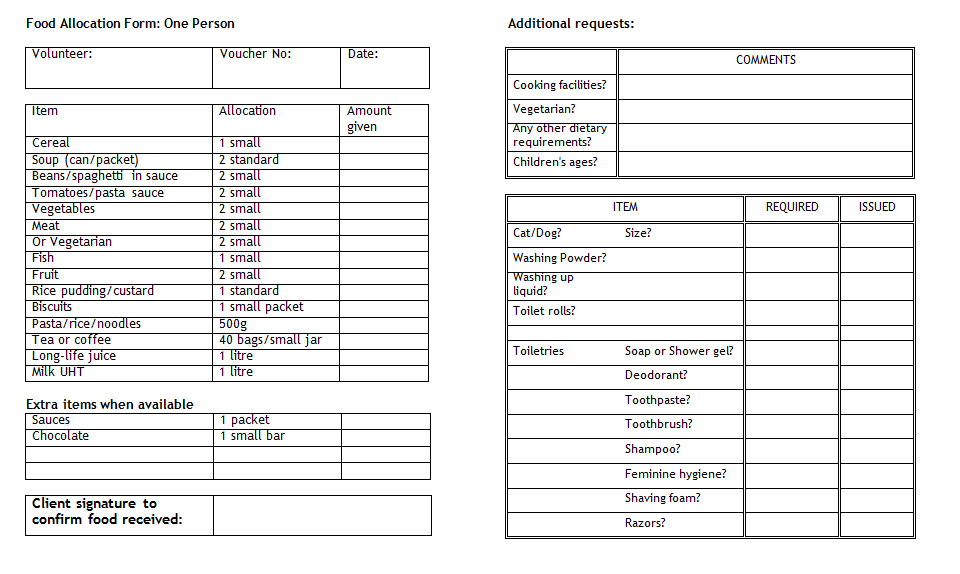
Food parcel single person packing list from the Trussel Trust


As I approached the end of my placement (which felt like it was ending just as quickly as it started!), we made plans to keep in contact about the ongoing development of the resources. We planned meetings with a food poverty group and with those running the food banks, and felt that good progress was being made. However, during the last week of my placement Covid-19 put a halt to our work. The last meeting that I attended in the council was geared towards how it could help to mitigate the impacts of the inevitable poverty that the virus would induce, as schools and food banks began to close, and many people expected to lose their jobs. Current projects at the council are now on ‘pause’ and those working in Public Health are tasked with devising solutions to the increasing number of problems that are arising from the pandemic.

At a time in which increasing numbers of people may need to access food banks and services, projects in Public Health and nutrition seem particularly relevant. I hope to be able to continue the project that we started during my placement in the future, taking into account new factors that may develop through this pandemic.

Maisie has worked at Newcastle University for over five years, collaborating with colleagues and researchers in Public Health England, charities such as Coeliac UK, international nutrition research centres, and the media.


Images:

1. Bob Castle, CC BY-SA 3.0, via Wikimedia Common

Friday, 29 January 2021

Bringing the voice of lived experience and community learning into research

Posted by Angela Broadbridge, Peer Research Lead, The Young Foundation (former Research and Evaluation Lead, Fulfilling Lives Newcastle Gateshead)

“There’s something really interesting in our data here, we don’t quite have the full picture, let’s talk to some people to puzzle it over more.”
This is something I hear myself or the team at Fulfilling Lives Newcastle Gateshead (FLNG) say really regularly. We’re an 8 year National Lottery Community Fund learning programme working to improve the lives of people facing multiple disadvantage and build a trauma-informed approach within the services that supports them. We have a wealth of data from supporting over 250 people locally, and we work with a team of Experts by Experience, people with lived experience working to bring about change across the systems they have been through, using their voices to be heard across different platforms.
Fulfilling Lives Newcastle Gateshead Experts by Experience Network co-design session

As the programme has developed our relationship with Fuse has changed and connections have grown, we now do much of our ‘puzzling over’ with Fuse colleagues! I joined Fuse as an associate member back in 2017 when I took up my post as research and evaluation lead for FLNG. I attended Fuse Quarterly Research Meetings to build up my contact base and learn from others operating in this interesting space between frontline practice and research and learning. As I began to see frontline practitioners come into those sessions, I invited some of our own frontline staff to join me to share their experience of working with people who have experienced complicated and challenging circumstances and struggled navigating systems.

I want to highlight some of our learning from building collaborative relationships through and with Fuse researchers, as this has proved to offer new platforms for the voice of lived experience not just to be heard in research, but to set research agendas and co-produce work alongside academics.

In 2018, Dr Sheena Ramsey (co-lead of the Fuse Healthy Ageing Research Programme) invited me to attend a Research Hub Initiative event with Public Health England and I pitched a seed grant funding idea with support from Fuse researchers. Our recently published work on deaths in the multiple complex needs community, an issue our Experts by Experience network encouraged us to explore, was borne out of this funding. We have since joined up with Sheena again in a new study identifying effective and sustainable interventions to improve the oral health of adults with severe and multiple disadvantage. This collaboration works because Sheena and other researchers associated with the study took the time to really get to know our programme, and our Experts by Experience network. Sheena visited us at the men’s accommodation project where we were based a few years ago, met some of our frontline staff and also built trusting relationships with the network, introducing us to academic and practice colleagues to further situate our programme learning within Fuse.

Brainstorm - what makes a good collaboration?
While this was happening, Prof Susan Carr (Fuse Associate Director), set up a meeting with her team at Northumbria University and FLNG peer researchers to talk about projects we were both working on and to explore collaborations. She also arranged for our peer researchers to present early findings from their work to Prof Kevin Fenton, Public Health Regional Director for London, and it was at this point that we started to see how people with lived experience could be involved in local research and practice beyond being participants. There were opportunities for genuine collaboration and learning together.

Fast forward to early in the pandemic and we were involved in two applications to the NIHR Applied Research Collaboration (ARC) for the North East and North Cumbria. One of these applications was exploring food insecurity with Fuse Associate Dr Steph Scott, and Kevin Dobson and Keith Gibson from FLNG’s research team set about exploring our own programme data around foodbank use. Our Lottery funded programme is quite unique in that we have a personal budget fund to use to support people on the programme with anything from their basic needs, including food and accommodation, to more creative uses like buying art materials or enjoying an afternoon at the cinema. Once again we had a ‘there’s something interesting here’ moment.

I sent Steph an email saying:
“we’ve worked with 259 people in Newcastle Gateshead over 6 years and of these 127 individual client records contained a reference to food insecurity or food poverty. We had 14 unique cases, interestingly all female, whose notes had 10 or more references to food poverty and we can see from the notes frequent references to benefits being suspended, people not eating, or missing the foodbank opening times.”
Working with partners to surface system barriers and solutions
The conversation that followed led to us talking to the Experts by Experience about food insecurity, they were similarly enthused by the topic and together we made a successful joint application to the Catherine Cookson Foundation within Newcastle University for a project exploring mutual aid during Covid-19. Using our Lottery funded programme learning and building on our experience co-producing research in other projects with Fuse researchers we are working with a group of Experts by Experience who have developed research questions to start a listening exercise with their peers around their experiences of food insecurity, mutual aid and Covid-19.

This relationship with Fuse is evolving and changing, and it now feels like a relationship truly rooted in the principles of co-production. Our team report that they feel their frontline experience is listened to and helps shape research projects, and our peer researchers are involved in numerous projects and have the confidence to approach Fuse researchers to develop new pieces of work building on the issues that are important to them and their communities. As our programme comes to an end in March 2022, the Experts by Experience network is now thinking about its legacy, we very much hope to continue to build on this strong foundation for collaboration and learning.

Friday, 15 January 2021

Tackling malnutrition during the pandemic and beyond

Posted by Megan McGuire, MSc Dietetics student, Teesside University

Part of our Fuse blog Student Series
The Fuse blog Student Series showcases posts by students who have been challenged to write a blog as part of their studies at one of the universities in the Fuse collaboration, the NIHR School for Public Health Research, or perhaps further afield. The authors may be new to blogging and we hope to provide a 'safe space' for the students to explore their subject and find their voice in the world of public health research.

As a dietetic student looking into public health and nutrition, it can often feel that the majority of policy focuses on the issue of obesity and ‘over-nutrition’. However, undernutrition, or malnutrition as it is more commonly referred to, remains a significant issue which is often overlooked in terms of policy.

Malnutrition is a term generally used to describe when your body is not getting the nutrients it needs to function properly. Good nutrition is important for every organ in our body, and therefore the consequences of malnutrition can be vast. This can include, increasing our risk to infections due to a weakened immune system and compromising our ability to regulate temperature, leading to hypothermia and potential organ failure of the heart and lungs (BAPEN, 2018a). Malnutrition can also make worse some of the things that cause it, such as social isolation, through its impact on mental health, including depression, anxiety and self-neglect (Public Health England, 2017). 

Malnutrition is unfortunately a common problem, particularly in those aged over 65, and is thought to affect over three million people in the UK at a cost of nearly £20 billion (Elia, 2015). In light of this, it is crucial that it can be easily detected within vulnerable groups, so that the devastating downstream consequences can be prevented.

Unfortunately, Covid-19 has made this all the more challenging. I know, from my personal experiences of remote dietetic placement working in the NHS, that one of the hardest things to find out via an online or telephone consultation is accurate height or weight information from the person on the other end of the line. This is not only pivotal for the majority of dietetic care, but also to the Malnutrition Universal Screening Tool (MUST), which can be used by any healthcare professional to determine someone’s risk of malnutrition (BAPEN, 2018b).

Current policy focusing on older adults, the people most vulnerable to malnutrition, tends to focus on strategies to promote ‘healthy ageing’, enabling wellbeing into later life (Age UK, 2011; WHO, 2012). There is, however, a lack of policy addressing malnutrition, specifically for those living in the community. Guidelines from the National Institute for Clinical Excellence (NICE) recommend screening for those within care homes and inpatient settings (NICE, 2012).

I feel that if more effort was put into community screening and early intervention, there would be fewer people admitted to hospital as a result of malnutrition, and therefore this is where public health efforts should be focused.

Whilst it may feel that Covid-19 is all anyone can talk about right now; I think we need to consider the impact it may be having on levels of malnutrition. Before the pandemic hit, there were already vulnerable people within the community who may have struggled to get out and about to do their shopping and care for themselves. The threat of a potentially deadly infection, for many, has driven them further indoors and into isolation. Alongside the direct effects of reduced access to food, due to venturing out less frequently and people ‘stockpiling’, there are also the psychological effects of the pandemic to consider. I know at times I have found lockdown challenging, so I can’t imagine how difficult it must have been for those living alone and feeling extremely isolated and vulnerable. Alongside issues of digital poverty too. Another point to consider is that these individuals may be less inclined to visit their GP or be seen by other healthcare professionals at these times, meaning that malnutrition is less likely than ever to be picked up.

The Patients Association Nutrition Checklist
So, what is the solution? We need to find a way to access the most vulnerable within society, at a time when staying indoors and away from others feels most safe. Public health policy needs to look at GP surgeries and ways in which they can target those who fall within the ‘at risk’ category. This could involve the use of digital technology, which has been shown to be successful in identifying malnutrition but may not be the best fit for those who can already feel isolated by a technology-driven world (Peek, Sujan & Scott, 2020). Another suggestion could be the rollout of the Patients Association Nutrition Checklist (2018), a less clinical, simple and easy to use tool which has been validated against MUST as a reliable method to detect malnutrition.

Whatever the approach, this is something I feel is underrepresented in the media and requires more public health attention in light of the pandemic. While I make sure to keep an eye on those around me who may be vulnerable to malnutrition, not everyone has that support network to fall back on and as a society, we ought to do more.


References:

Images:

2. 'The Patients Association Nutrition Checklist' courtesy of The Patients Association: https://www.patients-association.org.uk/blog/patients-association-nutrition-checklist

Friday, 8 January 2021

Now that's what I call blogging 2020: the Covid edition

Posted by Mark Welford, Fuse Communications Officer, Teesside University

It was business as usual for the Fuse blog in January 2020.  PhD student Kelly Rose told us about having sleepless nights thinking about school food and teenage diets; Coral Hanson and her co-authors channelled their inner Mr Motivator to consider whether exercise referral was fit for a new decade; and Angela Wearn asked if reaching the ‘hard-to-reach’ meant leaving traditional academia at the door?

So far so good… and then the ‘C’ word arrived and the world changed and with it the Fuse blog in the form of John Mooney’s frighteningly prescient post on the 5 February - Coronavirus: expect the unexpected in an unfolding emergency.

Last year we published posts about workplace health, tackling obesity through planning policy, the impact of commercial actors on health, food shaming, mental health, the emotional road to impact, Universal Credit, facing a Parliamentary Select Committee, inequalities, family carers of people living with dementia, International Men’s Day (yes, there is one!), and kicking Coca-Cola out of Christmas.

Our authors asked: 

  • Can your education, income or even your job affect your chances of receiving newer cancer treatments? 
  • Why is it so difficult to change our health habits? 
  • Does antibiotic prescribing penalise communities in most need? 
  • Would easy-read documents for all mean a more inclusive healthcare system? and;
  • What is the recipe for a happy retirement?

But it will come as no surprise that the 2020 chart of the top five most-read Fuse blog posts is dominated by one topic: Coronavirus, Covid-19 or just plain COVID.

Here are our chart-toppers of 2020:


5. Experts by Experience challenge us to create opportunities for them to take the lead in research

First up is our only non-Covid related entry in which Angela Broadbridge and Ged Hazlehurst from the Fulfilling Lives Newcastle Gateshead project write about co-producing research with people with lived experience of multiple and complex needs.

Page views: 1727.  Posted: 15 May 2020


4. COVID-19 has brought the “digital divide” to the fore

Gemma Wilson from Northumbria University explores how a lack of access to technology and wider support networks during the pandemic is significantly heightening inequalities.

Page views: 1839.  Posted: 29 May 2020


3. Coronavirus: expect the unexpected in an unfolding emergency

Up next is the aforementioned post by John Mooney, Locum Consultant in Public Health at NHS Highland and one-time specialist in the epidemiology of respiratory infectious diseases. Published days after the first confirmed UK cases, John's blog was prophetic in highlighting the potential for symptomless transmission, virus instability and divergent strains.

Page views: 1909.  Posted: 5 Feb 2020


2. This crisis has shown how many people were only just about managing

Our runner-up is Mandy Cheetham from Northumbria University writing about her experience with a community hub delivering food parcels, prescriptions and supporting vulnerable people during the pandemic.

Page views: 2019.  Posted: 9 May 2020


1. Working from home isn’t for everyone - here’s how to cope if you’re struggling

"Being isolated at home can be hard; it is easy to feel cut off from friends and co-workers, to feel out of the loop when it comes to work decisions and to feel stressed with how best to work when at home."  

During the first national lockdowns imposed by the UK governments, Annabel van Griethuysen from Tees, Esk and Wear Valleys NHS Foundation Trust, shared her tips on working from home. These include keeping a routine, eating and drinking well, having a completely separate space to work (if possible) which is tidied or hidden away at the end of the day, staying connected and reaching out to talk to your social circles if you feel anxious and stressed.

At a time when many people are again being asked to work from home it is apt that Annabel's post should take the crown as most popular blog in 2020.

Page views: 2106.  Posted: 9 April 2020


So there you have it, the top five Fuse blog posts from 2020.  All five received more page views than last year's number one, which is thanks to our loyal readers and fantastic contributors - thank you!  

Can we do any better in 2021?  If you fancy giving it a go, please find out what we are looking for and how to take part here.  All contributors receive a much sought-after Fuse badge, and the writer of the most read post wins a rare and coveted Fuse paperweight.*

Happy New Year!


*when we are allowed back in the office!


Images:

  1. "Now That's What I Call Music! 1991" by Brett Jordan is licensed under CC BY 2.0
  2. Courtesy of Fulfilling Lives Newcastle Gateshead: http://www.fulfillinglives-ng.org.uk

All page views correct at the time of writing.