Showing posts with label health inequalities. Show all posts

Friday, 11 September 2026

Strengthening partnerships to improve primary care in the Deep End

Posted by Dr Angela Wearn, Associate Member of Fuse and Advocacy and Engagement Lead for the Deep End Network North East and North Cumbria

In this blog, Angela reflects on what people living in some of the region’s most disadvantaged communities have told the Deep End Network about challenges they face when it comes to accessing primary care, including attending appointments, and what we can do to improve this.

The Deep End Network is a growing GP-led international movement that began in Glasgow in 2009 as a response to the ‘inverse care law’, which is that those who need care the most often struggle the most to access it.

The North East and North Cumbria Deep End Network was established in 2020, with support from Fuse, the Centre for Translational Research in Public Health, and the NIHR Applied Research Collaboration North East and North Cumbria, creating a space for practitioners working in areas of severe socioeconomic disadvantage to share experience, shape solutions, and influence how primary care can better meet the needs of the people it serves.

Funded by the North East and North Cumbria Integrated Care Board, the Deep End Network focuses on four core priorities:
  • Workforce: Building and retaining a well‑supported workforce in high‑need communities.
  • Education: Strengthening training at all levels so current and future health professionals understand health inequalities and access to opportunities
  • Advocacy: Ensuring Deep End practices and communities shape local and regional decisions on funding, access and service design.
  • Research: Evaluating Deep End initiatives to understand what works, why it works, and how effective approaches can be scaled to improve outcomes.
Since 2023, I’ve been working as Advocacy and Engagement Lead to build and strengthen partnerships between Deep End communities, practitioners and researchers, ensuring the experiences and perspectives of underserved patients and communities inform both our research portfolio and the wider support and initiatives we offer practices.

Over this time, additional funding and support from across NIHR infrastructure, including the NIHR Applied Research Collaboration North East and North Cumbria, NIHR Three Schools and NIHR Research Delivery Network, has further supported targeted involvement and engagement work with those living in Deep End neighbourhoods, the majority of whom have had no previous experience of involvement in research or service development.

Support through the NIHR Three Schools collaboration was made possible through membership of Fuse, which is part of the NIHR School for Public Health Research, one of the three NIHR schools within the collaboration.

What we’re hearing from Deep End communities

Many Deep End patients face multiple, overlapping challenges including low income, insecure housing, poor mental or physical health, caring responsibilities, trauma, or homelessness. These pressures make it harder to engage with primary care, even when people want to.

Through conversations, workshops, and community-led sessions, people have shared why engagement can feel difficult:
  • Personal pressures: the emotional and practical effort of attending can feel overwhelming and ‘too much’ on the day of the appointment.
  • Feeling unheard or stigmatised: which makes reaching out feel pointless.
  • Time and capacity: life can be busy, chaotic, and demanding, with health often taking a backseat.
  • Overwhelming contact routes: getting through to the practice or accessing a suitable appointment can feel impossible.
  • Negative past experiences: GP practices don’t always feel welcoming or safe.
Overall, I regularly hear that disengagement is rarely about disinterest, it’s about the collective barriers that build up and make staying connected to care difficult.

What communities say needs to change

Improving patient engagement in Deep End areas is complex. There is no single fix, and practices are working under significant resource constraints. But through our involvement work, communities have highlighted three priorities for investment and change that they feel would make a meaningful difference:
  • Improve connection and communication
  • Strengthen co‑design approaches
  • Build sustainable, community‑based partnerships
These priorities align strongly with national ambitions around personalised care, prevention, and reducing inequalities, and they reflect what people say would help them feel more able to engage with primary care as the wider system shifts towards more integrated neighbourhood-level working.

Moving forward together

The NHS encourages practices to work closely with Patient Participation Groups (PPGs), but Deep End practices face additional challenges: limited resources, diverse patient needs, and complex barriers to involvement. From the community perspective, awareness of PPGs is low, confidence is often limited, and many people are unsure whether their voice will genuinely matter. To support better partnership working, the Deep End Public Advisory Group identified three simple involvement principles that are easy to remember and act upon, and clear enough to come back to when things get busy or complex:
  • Make it easy
  • Make it worthwhile
  • Value patient experience
These principles are practical, community-informed and can be applied across a range of contexts to guide diverse involvement.

New one‑page resources for practices

To help bring these messages to life, we’ve co‑developed two infographics with Deep End patients, communities, and Nifty Fox. They distil community insights into quick, usable one-page resources that GP practices and other decision-makers can draw on to strengthen engagement and build more inclusive partnerships.

Supporting Patient Engagement in the Deep End: insights from the community
Working Better Together in the Deep End: patients and GP practices as partners

These resources will sit alongside a wider collection of materials, including a public‑facing animation and an illustrated impact report, which will be shared over the coming months. A celebration event is planned for early next year.


Why this matters

The Deep End Network exists because tackling health inequalities requires more than goodwill, it requires meaningful partnerships and system‑level commitment. These new resources are an important step in supporting practices and others to work alongside communities in ways that feel respectful, realistic, and rooted in the experiences of people who face the greatest barriers to accessing and influencing the care they receive.

We hope they support teams across the North East and North Cumbria and beyond to strengthen relationships, reduce barriers, and create primary care environments that are more responsive to the needs of communities most affected by health inequalities.

If you would like to know more about partnership working, co-production or our involvement work in the Deep End please contact Dr Angela Wearn (angela.wearn@newcastle.ac.uk)

Find out more about the Deep End Network

About the author
Dr Angela Wearn is Advocacy and Engagement Lead for the Deep End Network North East and North Cumbria and a Research Fellow with the NIHR Applied Research Collaboration North East and North Cumbria. She is also an Associate Member of Fuse, the Centre for Translational Research in Public Health.

Friday, 21 August 2026

Training tomorrow’s Public Health leaders: impact, innovation and prevention

Posted by Liz Morgan, Head of School for Public Health North East, NHS England

The North East Public Health Postgraduate Specialty Training Programme holds an event annually to showcase the work that has been done by trainees over the previous year. This annual showcase highlights how public health trainees in the North East are delivering practical, high‑impact work across the health and care system, demonstrating the value of prevention-led leadership at a time of increasing system pressure. It not only celebrates the tremendous work our trainees have been doing but also provides an opportunity to share that work with public health colleagues in multiple settings During this time, our trainees will have been immersed in communities, health and health-related systems and research environments, identifying challenges, designing solutions and implementing projects that demonstrate innovation and impact. The projects presented at our last meeting ranged from heath protection and health improvement to policy development and healthcare public health. Each one reflected the commitment, curiosity and compassion that defines our public health workforce.


Tackling air pollution through NHS leadership


Most NHS Trusts in the North East employ at least one public health consultant, valuing the broad benefits that this can bring, but also providing greater capacity for public health training. Dr Laura Keast had been undertaking a placement in Northumbria NHS Trust, implementing the Clean Air Hospital Framework and demonstrated the value of collaboration between public health and sustainability teams. Air pollution remains the single greatest environmental threat to public health in the UK, contributing to an estimated 30,000 deaths annually and worsening health inequalities. By making air pollution a tangible and locally relevant issue through accessible monitoring of nitrogen dioxide levels and clear health messaging, the initiative has generated engagement and momentum for action. Importantly, the project highlighted that public health leadership, data expertise, powerful health messaging and alignment with national policy levers are critical in overcoming uncertainty and organisational resistance to change.

Reducing missed outpatient appointments for children

Dr Mark Riley presented a service evaluation undertaken at South Tees NHS Trust exploring why children are not brought to outpatient appointments, an issue with significant implications for health outcomes and system efficiency. Using surveys and follow-up telephone calls, the evaluation identified five key themes:
  • appointment timing
  • forgotten appointments and reminders
  • administrative barriers
  • health literacy
  • cost of attendance.
Forgotten appointments were the most common reason for non-attendance, with parents strongly favouring clearer and more frequent text reminders. Difficulties rearranging appointments, confusing letters and limited awareness of travel cost reimbursement schemes further contributed to missed care. The findings underscore how relatively small, system-level changes, such as health-literate communications in multiple languages and flexible appointment scheduling to include evenings, can reduce inequalities and improve service use. Finding a champion in the organisation to enable change was also critical.

How leaders make difficult priority-setting decisions

As pressures on the NHS intensify, difficult decisions about how to allocate limited resources are unavoidable. Dr Tom Seasman explored how senior health leaders justified priority-setting decisions. Qualitative in‑depth interviews with leaders across the English health system show broad support for prevention and reducing health inequalities. However, when faced with real-world trade-offs, decisions often favour short-term frontline clinical care over long-term preventative investment and leaders differ in their responses. Clinical leaders often prioritise immediate need and the “rule of rescue”, while those approaching the same problem from a public health perspective place greater emphasis on maximising population health gains through prevention. Political constraints, emotional proximity to patients and fragmented funding structures frequently limit leaders’ ability to shift resources from acute care to prevention, despite widespread recognition that long-term sustainability depends on doing so. These findings raise important questions about how the health system can better support leaders to make transparent and ethical trade-offs.

Policing and public health: prevention in action

Prevention also featured strongly in work exploring collaboration between policing and public health. This is important because of shared commitments to improve lives, reduce harm, reduce unnecessary demand on services, reduce vulnerability, improve equity and maintain public trust. Since the publication of a national consensus statement in 2018, prevention has become more explicitly embedded within policing policy and inspection frameworks. A 2025 review concluded that, while the original vision remained relevant, a refreshed consensus was needed to reflect current challenges and language. Kylie Murrell led on this national project, chairing the policing and public health collaborative, leading on the re-drafting of the document and sign off and associated ministerial briefing. The work highlights both the appetite within policing to engage more fully in prevention and the ongoing need for public health professionals to support cross-sector partners to identify upstream opportunities to reduce harm, vulnerability and demand. It's also an excellent example of how our trainees have led on national initiatives.

Supporting wellbeing within the public health workforce

Alongside the ongoing system-level challenges, attention to the wellbeing of the public health workforce itself is increasingly recognised as essential. Vineeta O’Key reflected on the work the trainees had been doing to support their own wellbeing and on how a Wellbeing Away Day could demonstrate how evidence-based wellbeing approaches could be embedded within training and professional development. Grounded in the “Five Ways to Wellbeing”, the day prioritised connection, learning, physical activity and engagement with nature through volunteering with Durham Wildlife Trust. Feedback highlighted the value of protected time for relationship-building, reflection and compassionate leadership, reinforcing the role of wellbeing as both a personal and professional competency in public health practice.

Julie Lowe presented her experience of travelling to Canada and the Netherlands on a Churchill Foundation fellowship. The Foundation funds approximately 100 Fellows each year to travel overseas to explore an issue of societal importance. This project focused on community interventions to improve the health and wellbeing of unpaid caregivers, who, as a population, experience poorer mental and physical health outcomes known informally as the ‘carer burden’. She shared reflections from her own experience as a young carer and motivation for choosing a career in public health. Findings from her experience included the importance of listening to diverse groups of carers to understand their needs and preferences, and the need for interventions that reduce carer burden rather than responding to health needs as they arise.

Taken together, these projects reflect a common theme: public health impact is maximised through leadership, collaboration and a commitment to prevention, even in constrained systems. Our trainees are already having an impact in their placements and communities by shaping national priorities, supporting workforce wellbeing and building partnerships beyond health. Creating spaces like this conference where recent projects and ideas can be shared, and challenges are explored are vital and demonstrates how public health continues to be pivotal in navigating complexity and working towards more equitable and sustainable futures. I would strongly encourage all of our public educators and senior public health colleagues to attend this event. As Public Health influencers, the task of considering, adapting and altering these ideas and interventions for the benefit of the populations we serve rests with us.

Wednesday, 19 March 2025

How our ‘test & learn’ prototypes are strengthening Social Prescribing

Posted by Ang Broadbridge, Head of Implementation at Ways to Wellness, on #SocialPrescribingDay

Evaluation is often something that happens at the end of a project, but what if we built learning into the process from the very start?

At Newcastle-based charity Ways to Wellness, we believe that embedding a culture of learning from the outset helps social prescribing link workers share real-time insights, refine approaches, and ultimately improve support for the communities we serve.

One area where this model has been used is in maternal mental health


Co-designing for impact

A core part of our work is connecting with local communities to shape and refine prototypes that align with our mission:
  • Improving health and wellbeing
  • Tackling health inequalities
  • Reducing demand on NHS services
To ensure our link workers could share learning, develop key messages, and highlight gaps in services, we adopted the Learning Communities model. As described in the Learning Communities Handbook, these are:
"A group of peers who come together in a safe space to reflect and share their judgements and uncertainties about their practice and to share ideas or experiences to collectively improve."
To embed this approach into recruitment and training, we:
  • Included an expectation for link workers to actively engage in Learning Communities
  • Encouraged participation in ‘test and learn’ approaches
  • Provided ongoing support and facilitation to foster a sense of ownership and belonging.
This approach helped link workers collaborate across different host organisations, spanning locations across the North East and North Cumbria.

Extending learning into maternal mental health

One area where this model has been used is in maternal mental health. After eight months of Learning Community meetings, we expanded this approach through a series of external learning events. These events:
  • Shared early insights from our maternal mental health prototypes
  • Brought in new partners to co-develop next steps
  • Strengthened cross-sector collaboration
A key learning was that while social prescribing is well known in GP practices, it was midwives and health visitors who played a crucial role in referring parents to our prototypes - roles that hadn’t previously collaborated with link workers.

By opening up new referral pathways, we helped develop best practices for integrating link workers into maternal healthcare settings.

Turning insights into action

Our Learning Communities aren’t just discussion spaces - they drive change. Link workers use them to:
  • Identify barriers in accessing social prescribing
  • Test new ways to connect people with support
  • Share insights at external events and policy discussions
The impact has been tangible. For example, after testing different approaches, some link workers are now based in health appointment clinics - an innovation that has improved system-wide connectivity and access to services.

Why this approach matters

By embedding a culture of continuous learning, we are:
  • Strengthening partnerships across health and care sectors
  • Ensuring services are designed with communities, not just for them
  • Maximising the impact of social prescribing
At Ways to Wellness, we believe that the voluntary sector, healthcare services, and community organisations must work together to tackle health inequalities.

That’s why we’re committed to testing, learning, and adapting - so that social prescribing continues to evolve, improve, and reach the people who need it most.

Find out more at: waystowellness.org.uk


Image credits: Ways to Wellness Limited company number: 08798423

Friday, 27 September 2024

Amplifying voices to tackle inequalities in South Asian and Muslim communities

Posted by Zeibeda Sattar, Assistant Professor in Health Policy, Northumbria University

L-R: Greta Defeyter, Humaira Khan and Zeb Sattar 
I recently had the opportunity to chair the Health Inequalities Symposium hosted by the Centre for Health and Social Equity (CHASE) at Northumbria University, in collaboration with Fuse. It was an incredible event that brought together over 100 people, including researchers, policymakers, healthcare providers, and community members, all focused on tackling the pressing health challenges facing South Asian and Muslim (SAM) communities. The main goal was clear: to find ways to bridge the gap between research and real-world impact.

The presentations were enlightening and underscored how critical it is to engage with minority communities effectively to shape public health services. Each speaker highlighted a different, but equally important, health issue impacting SAM communities. Public partner Humaira Khan, who co-chaired the symposium, pointed out that the mental health challenges facing South Asian and Muslim are often misunderstood and stigmatised. Hearing her talk about the need for culturally competent healthcare really hit home. Her words - “researchers are warriors; they don’t fight for themselves - they amplify the voices of the people” - perfectly captured why events like this matter.

“researchers are warriors; they don’t fight for themselves - they amplify the voices of the people” 

Humaira Khan, public partner


Dr Sarah Croke from the University of Manchester spoke about the language and cultural barriers that often lead to untreated health issues. This can leave community members struggling because healthcare services aren’t designed with South Asian and Muslim needs in mind. Dr Saeed Ahmed from Sunderland Royal Hospital took on the tough topic of organ donation disparities. He pointed out the harsh reality: SAM communities are in desperate need of organ transplants but are also among the least likely to donate. His call to raise awareness and educate was powerful, especially when he reminded us that one donor can change up to nine lives.

There were also discussions about everyday barriers that many of us face but rarely see addressed. Professor Defeyter from Northumbria University talked about the lack of culturally appropriate meals, like halal options, in schools. It was a reminder of how even things like food choices can create a sense of exclusion for our children and why legal changes to recognise cultural diversity are long overdue.

I found Simon Luddington’s (SearchNewcastle) presentation about the West-End Befrienders project particularly inspiring. It’s easy to forget how isolating language barriers can be and how vital social connections are for our wellbeing. Their work in bringing people together, especially in helping with access to primary care and breaking down isolation, felt like a model that should be replicated.

One of the more challenging discussions was around drug and alcohol use in our communities. Lydia Lochhead’s (Northumbria University) research laid bare the stigma that prevents so many from seeking help. It’s a tough conversation to have, but hearing about Mushtaq Dakri’s community-led approach to addiction support was a beacon of hope. They offer a holistic service - combining therapy, physical activity, and spirituality - and it’s designed by and for the SAM community. Knowing there’s a women-only support space now available shows their commitment to evolving and meeting community needs.

Fuse Associate Director Dr Floor Christie and Dr Rawand Jarrar from Sunderland University, wrapped up the day with their work on improving cancer screening uptake among Muslim women. Their workshops have reached over 260 women, and it’s encouraging to see how culturally sensitive approaches can genuinely improve health outcomes. This was a reminder of how vital it is to build services that reflect our communities.

As I reflect on the symposium, it’s clear to me that these health inequalities are not just about accessing services - they’re about how these services are designed and delivered. The urgency to address these gaps cannot be overstated. The event reinforced the need for services that truly understand and respect South Asian and Muslim communities, going beyond just offering a service to creating environments where people feel welcomed, understood, and valued.

Leaving the symposium, I felt hopeful. Change is possible, but it won’t happen without consistent engagement with our communities. Trust needs to be built, and community voices must be represented and acted upon. The gap between research and impact can be bridged if we keep pushing for culturally relevant, accessible, and respectful health services.

Plans are already in place for a follow-up symposium in November, focusing once again on the health inequalities that continue to affect SAM communities. I urge everyone to get involved. This is our chance to be part of the change and to make our voices heard in the ongoing fight for a more equitable health system. Sign-up details will be shared soon, and I hope to see more of us there - because turning these conversations into action is how we create a healthier future for all of us.

Friday, 13 September 2024

How can Local Authorities help shape healthier food environments?

Posted by Amelia Lake, Claire O'Malley and Helen Moore, Fuse researchers from Teesside University

This week I joined other health professionals across the country in signing an open letter from the Obesity Health Alliance (OHA) to the Prime Minister, giving our support for new policy reforms, allowing the planning system to better support the creation of healthy, active local communities and reduce health inequalities. The letter was issued alongside the OHA's Local Government Position Statement: “Empowering Communities to Create Healthier Local Food Environments”, which contains a list of recommendations and a supporting package of evidence.

In support of the OHA statement paper and on the back of the news that the government plans to ban junk food TV adverts before 9pm next year, here we highlight the need to make it easier for local authorities to control their local food environments.


Why we need to act now

It’s essential to create healthier environments that make it easier for people to access nutritious food and engage in physical activity. With the cost of living rising, more people are facing food insecurity, and obesity remains a major health issue. Local authorities have a crucial role in shaping healthier communities, but they face challenges due to funding cuts. Despite these difficulties, professionals across the country are working hard, but they need clearer national policies to support their efforts.

The role of National Planning Guidance

Planning guidance should clearly prioritise public health. While policies often focus on individual responsibility, local governments can work with their communities to promote healthier lifestyles. Our research has shown how local authorities can shape healthier environments by collaborating with various stakeholders, from community members to policy makers.

Everyone’s responsibility


Creating healthy food environments requires collaboration among many professionals within local governments. When it comes to handling appeals for fast-food outlets, our research found that good communication between teams is key to defending decisions. It’s also important to understand how fast-food outlets affect communities and health over the long term. To improve the process, professionals should be trained in accessing relevant data and records.

Using regulations to improve the food landscape

Local authorities can use planning regulations to limit the number of fast-food outlets and promote healthier options. For example, in North East town Gateshead, limiting new fast-food outlets near schools, in areas with too many, or in places with high childhood obesity rates has reduced fast-food outlet numbers by 17.5% in just four years. This shows how strategic planning can make a real difference in promoting healthier food choices.

Working with the planning inspectorate

The National Planning Policy Framework supports the idea of “healthy communities,” and local governments can reject fast-food applications if they threaten local health goals. However, these decisions are often appealed, and the Planning Inspectorate makes the final decision. Our Fuse research shows that having a Local Plan in place helps local authorities reject such applications, but even with additional planning documents, success isn’t guaranteed. It's important for new planning guidelines to support public health and ensure that the Planning Inspectorate works with local authorities to meet health priorities.

Regulating outdoor food advertising

We support extending regulations on unhealthy food and drink ads beyond TV and online to outdoor spaces like bus stops. After London banned junk food ads on public transport, local governments began reviewing their advertising policies with the help of Sustain: the alliance for better food and farming. Our research in the North East found that almost half of bus shelter ads were for food, and 35% of those were for unhealthy options. Many of these ads appeal to children, which is concerning. Although local governments face challenges due to complex contracts with advertisers - and research has explored the advertising of unhealthy commodities (e.g. tobacco, alcohol, less healthy foods and gambling) - more work is needed to reduce the impact of unhealthy advertising.

The changing food landscape

A recent study in North East England showed that after a new fast-food outlet opened, visits by 11- to 16-year-olds increased significantly within the first nine months. The young people said they were attracted by the taste, low prices, socialising and free Wi-Fi. While this isn’t covered by current fast-food restrictions, it shows the need to look at the entire food system and where outlets are located. Policies that prevent students from leaving school during lunch could also help reduce fast-food consumption.

Another growing trend is "dark kitchens," which only prepare food for delivery services like Deliveroo and Uber Eats. While these kitchens bring economic benefits, they raise public health concerns, especially in low-income areas. Local authorities need to stay informed about this trend and address the challenges it presents, such as the increase in unhealthy food options. Some professionals worry that current regulations for fast-food outlets don’t work well for dark kitchens, so there’s a need to adapt the system to ensure public health is protected.

Monitoring and evaluation

It's important for local authorities to regularly review the food environment and assess how well their policies are working. By collecting and analysing data, they can identify areas for improvement and make sure their strategies are effective and responsive to community needs.

Focusing on these areas will help local governments create environments that support healthy choices and improve the overall wellbeing of their communities. With thoughtful planning and strong community involvement, they can significantly impact public health. To do this effectively, local authorities need clear understanding of planning policies, support from senior management, adequate staff, and the right resources to handle cases efficiently.


Amelia Lake is Professor of Public Health Nutrition at Teesside University, Associate Director of Fuse, the Centre for Translational Research in Public Health, a dietitian and public health nutritionist.

Dr Claire O'Malley is a Research Associate at Teesside University and a Fuse Associate member

Helen Moore is an Associate Professor at Teesside University and a Fuse Associate member


Photo by Erik Mclean on Unsplash

Wednesday, 11 September 2024

Food insecurity in pregnancy is putting women’s health at risk and babies at a health disadvantage. That is unfair and unjust

Posted by Zoë Bell, Postdoctoral Research Fellow, King’s College London

In the three years since we started this project a lot has changed, and nothing has changed at the same time. Just as the pandemic was leaving a shadow behind us, we entered a new chapter of social and economic challenge; notably, the Russian invasion of Ukraine and Brexit fuelling a cost-of-living crisis with huge impacts on our food system and food prices. These events, in their own unique ways, have left households more vulnerable to experiencing poverty, and the topic of this blog, food insecurity.

During this time, we’ve witnessed food insecurity become a more prominent feature in the news with the help of celebrity advocates and mutual aid groups which brought communities together to support one another. Headline examples are Marcus Rashford’s campaign supporting the extension of free school meals over the summer holidays, and most recently, Taylor Swift’s donation to food banks in cities across the UK as part of her tour. Within the context of a decade long erosion of the social security safety net, the charitable sector has stepped in to provide food relief; but it’s clear this is just a sticking plaster.


While temporary economic, social and nutrition policies were put in place during the pandemic to support vulnerable families, long-term commitment has been lacking.

Time is ticking and it is the most vulnerable who are paying the price. Indeed, pregnancy is a time when the consequences of inadequate support come at a premium cost.

We know how important it is for pregnant women to eat a nutritious and well-balanced diet for their own health and for their developing baby. This is where our research fits in. We set out to pull together all the available evidence to explore whether there are differences in pregnancy risks for women and babies when they experience food insecurity.

Our two new reviews of the evidence around food insecurity in pregnancy and the links with maternal weight, diet, and pregnancy health show worrying results, including both physical and mental health risks. While we were expecting to see some health implications, the extent of the risk for poorer health was shocking. Pregnant women experiencing food insecurity were significantly more likely to have poor mental health, obesity, poor quality diets, develop Gestational Diabetes and dental problems.

Infographic to translate the review findings co-designed with experts by experience during an engagement workshop in Newcastle
Upon Tyne, North East England. Funded by Tilly Hale a Newcastle University Faculty Medical Sciences Engagement fund.


Noticeably, these reviews lacked studies from the UK with studies mainly from the USA. You might ask does this matter? Yes. Why? Because the USA has long-standing nutritional support for pregnant women, with evidence of having beneficial impacts on women's diet and health. This embedded support might have reduced or completely masked some of the associations that food insecurity has with pregnancy risks reported in these studies. Whereas in the UK nutritional programs are not as extensive and women lack support. This means we might find that the risks are worse and the need for support is greater than we currently think it is in the UK.

We acknowledge these reviews are based on observational data, exploring association rather than causation. Women experiencing food insecurity are likely living with multiple other causes of stress that could be contributing to food insecurity and pregnancy risks. Nevertheless, we see from the evidence to date that these women are at risk and need more support. Our ongoing work exploring experiences of food insecurity during pregnancy also suggests that current support initiatives are not doing enough, and further policy-related intervention is required, further emphasising the need for action now.

Our new reviews show that food insecurity during pregnancy contributes to health inequalities, putting women’s health at risk, and babies at a health disadvantage from before a they are born. For example, when babies are exposed to gestational diabetes or maternal obesity, they are more likely to develop type 2 diabetes or obesity themselves later in life. That is unfair. That is unjust. So, we ask, how much more evidence is needed before urgent policy action is taken to mitigate food insecurity?

Much more support from government is needed to make sure that women and babies are protected from food insecurity during pregnancy. Only time will tell if tides will turn under this new Labour government.

So, what do we suggest?

First, an uplift in the value of the Healthy Start scheme, a policy directly related to nutrition during pregnancy and early years. Second, greater integrated care across multiple sectors for women during the pregnancy period. Thirdly, considering the wider interlinked, structural barriers for families living in poverty (and based on our broader research program) removal of the two-child benefit cap, continued expansion of childcare support and of free school meals. These policies would relieve financial pressures on households with young families.

In the meantime, watch this space as our research team has two ongoing reviews exploring pregnant women and people's experiences of food insecurity and its relationship with breastfeeding and infant feeding. Some of our other ongoing studies are exploring the experiences, risks and support needs of women during pregnancy and in the postnatal period after birth, and their families across a diverse UK population in Gateshead, Coventry, Middlesbrough, Lambeth and Bradford.

If you are inspired to help add evidence and advocate for food security amongst mothers and children, then please consider becoming a member of our Nourishing Futures Network. This was established by Fuse members working with international colleagues. The network’s mission is to lead knowledge exchange and generate knowledge in this emerging field around food insecurity before and during pregnancy and in the first 2001 days of life.


Find out more

This research has been summarised in the following:

Friday, 22 March 2024

"We need happy memories"

How people who have experienced homelessness are redesigning support

Professor Monique Lhussier & Dr Christina Cooper from Northumbria University, and an Experts by Experience panel

Fuse researchers at Northumbria University were recently awarded £1.4m for a project looking to understand connections between trauma, health and homelessness in the North East. Here the research leads share how they have previously worked to embed community voices to improve health and reduce disparities for people with experience of homelessness.

The link between trauma and homelessness has been well documented, with recent evidence showing that 94% of people experiencing homelessness have experienced trauma. In the majority of cases the trauma was complex and reoccurring, with 65% having experienced four or more traumatic experiences.


In 2023 we received funding from the Arts and Humanities Research Council to develop a network to better support people who had experienced homelessness. We were fortunate to work with eight Experts by Experience (EbEs), or Experts by ‘Disaster’ as Barnie (one of our EbEs) suggested; people who had experienced homelessness, and the complex multiple needs and exclusions that frequently co-occur. The nine months project aimed to develop integrated ways of working, embedding community voices into the system to improve health and reduce disparities for People with Experience of Homelessness (PEH).

Discussions, which were led by EbE throughout the project, reiterated that trauma was common and often started in childhood, and followed by further re-traumatising events. Karl commented that while he remembered in vivid detail what had happened to him as a child, he often could not recall what he had been doing last week, highlighting the lasting impacts of trauma. Further discussions highlighted negative impacts throughout life, from relationships, education, employment to mental illness, suicide and addiction.

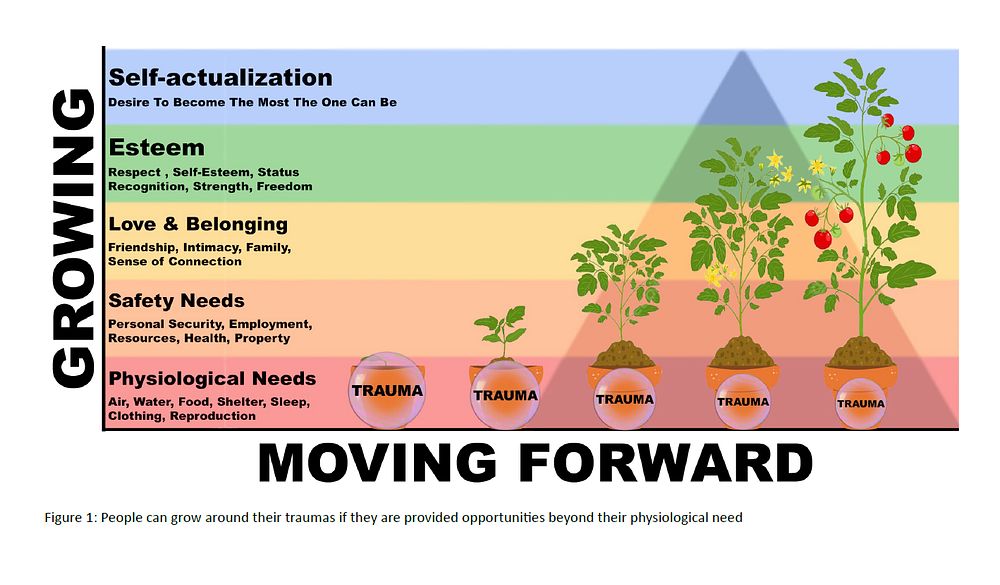
We reflected as a group that PEH are often viewed through a lens that considers only their immediate needs; shelter, clothing, food, and healthcare. Drawing on Maslow’s hierarchy of needs we considered that only the bottom two tiers are the most consistently met, but belonging and esteem much less so. The Experts by Experience felt that people need to be given a chance to grow in more holistic ways across all tiers of the hierarchy in order to become healthier and happier.

Tonkin’s model of grief proposes a way to see a happy and meaningful future focusing on growth around the grief. From these discussions, we collaboratively designed the graph below, which superimposes Maslow’s hierarchy of needs with and adapted version of Tonkin’s, in a model to inform ongoing and future work.

We have begun to explore this model through three core project strands:
  1. an innovation fund for which EbE were responsible;
  2. participation in an accredited Northumbria University module, and
  3. through understanding the impacts of involvement with the project.
The innovation fund pilot involved the development and implementation of five creative projects providing sustainable and varied opportunities for self-care, learning, and physical activity for People with Experience of Homelessness. One of those, the Hope Project, gave opportunities for 189 PEH to take part in new creative, social, or physical activities. Steven designed the Hope Project on the premise that ‘people need happy memories’, which those who have experienced trauma do not always have, to draw on when the going gets tough. Barnie explained that often people lose the motivation and ability to cook for themselves when they have lived on the streets. He designed cookery classes with a train the trainer model, meaning that many people have since benefitted from eating healthier food that they had cooked themselves. Lee set up a bike repair workshop so people can take part in physical activity and be more self-sufficient.


Being given the opportunity to manage a budget, help others and having the status of university student (“I have been called many things; it was nice being called a student!”), stood out as having had a positive impact for many of the Experts by Experience. Lee and Porl said that opportunities to shape the project and develop their skills as researchers led to them feeling trusted and valued as equal members of the project team. Further to this, involvement in the project gave a sense of purpose and belonging, and increased confidence for many EbE.

This supported the notion that it is possible to grow around trauma when we attend to people’s experiences, hopes, talents, potentials and ambitions, as well as their basic needs. It also challenged us, as researchers, to think of research not solely as a detached enterprise, but as an inherent part of a system that can support people to grow and have more positive and valuing experiences.

*This blog has been written in memory of Ben


References:
Image:
  1. Photo by Matt Collamer on Unsplash